Please wait while the formulary information is being retrieved.
Drug overview for JAKAFI (ruxolitinib phosphate):
Generic name: RUXOLITINIB PHOSPHATE (RUX-oh-LI-ti-nib)
Drug class: Antineoplastic - Janus Kinase (JAK) Inhibitors
Therapeutic class: Antineoplastics
Ruxolitinib phosphate, a selective inhibitor of Janus kinase (JAK) 1 and 2, is an antineoplastic agent.
No enhanced Uses information available for this drug.
Generic name: RUXOLITINIB PHOSPHATE (RUX-oh-LI-ti-nib)
Drug class: Antineoplastic - Janus Kinase (JAK) Inhibitors
Therapeutic class: Antineoplastics
Ruxolitinib phosphate, a selective inhibitor of Janus kinase (JAK) 1 and 2, is an antineoplastic agent.
No enhanced Uses information available for this drug.
DRUG IMAGES
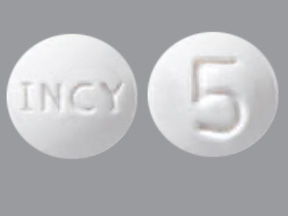 JAKAFI 5 MG TABLET
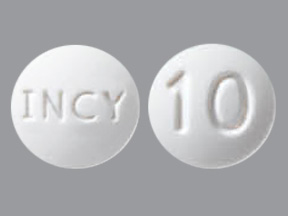 JAKAFI 10 MG TABLET
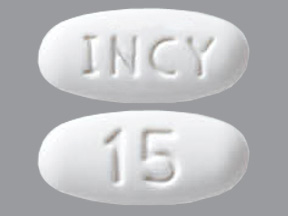 JAKAFI 15 MG TABLET
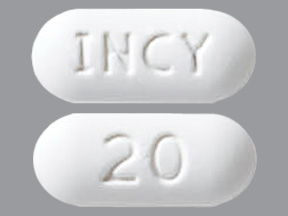 JAKAFI 20 MG TABLET
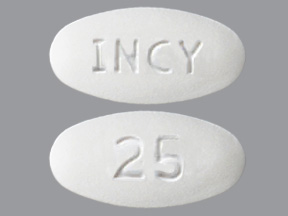 JAKAFI 25 MG TABLET
The following indications for JAKAFI (ruxolitinib phosphate) have been approved by the FDA:
Indications:
Chronic graft-versus-host disease
Graft-versus-host disease
Myelofibrosis
Polycythemia vera
Professional Synonyms:
Chronic graft versus host disease
Chronic GVHD
Graft versus host disease
Graft versus host reaction
Graft vs. host disease
GVH disease
Indications:
Chronic graft-versus-host disease
Graft-versus-host disease
Myelofibrosis
Polycythemia vera
Professional Synonyms:
Chronic graft versus host disease
Chronic GVHD
Graft versus host disease
Graft versus host reaction
Graft vs. host disease
GVH disease
The following dosing information is available for JAKAFI (ruxolitinib phosphate):
Dosage of ruxolitinib phosphate is expressed in terms of ruxolitinib.
Dosage reductions may be considered based on platelet count without interrupting therapy in patients with a baseline platelet count >=100,000/mm3(see Table 1) and in patients with a baseline platelet count of 50,000 to <100,000/mm3(see Table 2). However, temporary interruption of therapy is necessary in patients with a baseline platelet count of >=100,000/mm3 if platelet count decreases to <50,000/mm3 or ANC decreases to <500/mm3.
Table 1. Recommended Dosage Reduction for Platelet Count in Patients with Baseline Platelet Count >=100,000/mm3
Current Platelet Count and Recommended Ruxolitinib Dosage Ruxolitinib Dosage 100,000 to <125,000/mm3 on a 20 mg twice daily ruxolitinib dosage of 25 mg twice daily 100,000 to <125,000/mm3 on a 15 mg twice daily ruxolitinib dosage of 20 mg twice daily 100,000 to <125,000/mm3 on a No dosage adjustment ruxolitinib dosage of 5, 10, or 15 mg twice daily 75,000 to <100,000/mm3 on a 10 mg twice daily ruxolitinib dosage of 15, 20, or 25 mg twice daily 75,000 to <100,000/mm3 on a No dosage adjustment ruxolitinib dosage of 5 or 10 mg twice daily 50,000 to <75,000/mm3 on a 5 mg twice daily ruxolitinib dosage of 10, 15, 20, or 25 mg twice daily 50,000 to <75,000/mm3 on a No dosage adjustment ruxolitinib dosage of 5 mg twice daily
Table 2. Recommended Dosage Reduction for Platelet Count in Patients with Baseline Platelet Count 50,000 to <100,000/mm3
Current Platelet Count Recommended Ruxolitinib Dosage Reduction 25,000 to <35,000/mm3 AND decline in Reduce ruxolitinib dosage by 5 mg platelet count is <20% during the once daily prior 4 weeks For patients currently receiving 5 mg once daily, maintain dosage 25,000 to <35,000/mm3 AND decline in Reduce dosage by 5 mg twice daily platelet count is >=20% during the prior 4 weeks For patients currently receiving 5 mg twice daily, decrease dosage to 5 mg once daily For patients receiving 5 mg once daily, maintain dosage
In patients with a baseline platelet count of >=100,000/mm3, temporarily interrupt ruxolitinib therapy if platelet count decreases to <50,000/mm3 or ANC decreases to <500/mm3. When platelet counts improve to >50,000/mm3 and ANC improves to >750/mm3, ruxolitinib may be resumed. When restarting, begin with a dosage at least 5 mg twice daily below the dosage at interruption and follow the manufacturer's guidelines for the maximum allowable dosage that may be used when restarting treatment (see Table 3).
Table 3. Maximum Restarting Dosage of Ruxolitinib Following Interruption of Therapy for Thrombocytopenia in Patients with Baseline Platelet Count >=100,000/mm3
Current Platelet Count Maximum Recommended Dosage Following Interruption of Therapy >=125,000/mm3 Maximum dosage of 20 mg twice daily 100,000 to <125,000/mm3 Maximum dosage of 15 mg twice daily 75,000 to <100,000/mm3 Maximum dosage of 10 mg twice daily for at least 2 weeks; if stable, may increase to 15 mg twice daily 50,000 to <75,000/mm3 Maximum dosage of 5 mg twice daily for at least 2 weeks; if stable, may increase to 10 mg twice daily <50,000/mm3 Continue to withhold therapy
If ANC <500/mm3 occurs, temporarily interrupt ruxolitinib therapy; when ANC improves to >=750/mm3, ruxolitinib may be resumed at the higher of the following dosages: 5 mg once daily; or 5 mg twice daily below the highest dosage in the week prior to the treatment interruption.
In patients with a baseline platelet count of 50,000/mm3 to <100,000/mm3, temporarily interrupt ruxolitinib therapy if platelet count decreases to <25,000/mm3 or ANC decreases to <500/mm3. When platelet counts improve to >35,000/mm3 and ANC improves to >750/mm3, ruxolitinib may be resumed at the higher of the following dosages: 5 mg once daily; or 5 mg twice daily below the highest dosage during the week prior to the treatment interruption.
If clinical response is considered insufficient in patients with a baseline platelet count of >=100,000/mm3, the dosage of ruxolitinib may be increased in increments of 5 mg twice daily up to a maximum of 25 mg twice daily if all the following conditions have been met: failure to achieve a reduction from pretreatment baseline spleen size of either 50% in palpable length or 35% in volume as measured by CT or MRI; platelet count >125,000/mm3 at 4 weeks; platelet count never reduced to <100,000/mm3; ANC >750/mm3.
Based on limited clinical data, long-term maintenance with ruxolitinib at a dosage of 5 mg twice daily has not shown response; therefore, continued long-term use of the drug at a dosage of 5 mg twice daily should be limited to patients in whom benefits outweigh the potential risks.
If clinical response is considered insufficient in patients with a baseline platelet count of 50,000/mm3 to <100,000/mm3, the dosage of ruxolitinib may be increased in increments of 5 mg daily up to a maximum of 10 mg twice daily if the following conditions have been met: platelet count has remained >=40,000/mm3 and has not decreased by more than 20% in the prior 4 weeks; ANC is >1000/mm3; and the dosage of ruxolitinib has not been reduced or withheld due to an adverse event or hematologic toxicity in the prior 4 weeks. Continuation of ruxolitinib beyond a duration of 6 months should be limited to patients in whom the benefits outweigh the potential risks.
Do not increase the ruxolitinib dosage during the first 4 weeks of therapy or more frequently than every 2 weeks.
If the size of the spleen does not reduce or symptoms do not improve following 6 months of therapy with ruxolitinib, the drug should be discontinued.
If a hemorrhagic event requiring intervention occurs during ruxolitinib therapy in patients with myelofibrosis, interrupt treatment regardless of the current platelet count. If the hemorrhagic event resolves and the underlying cause of bleeding is controlled, consider resuming ruxolitinib at the dosage used prior to treatment interruption. If the hemorrhagic event resolves but the underlying cause persists, consider resuming ruxolitinib at a reduced dosage.
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. The initial dosage of ruxolitinib should be reduced based on baseline platelet count. (See Table 4.) Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
Table 4. Recommended Initial Dosage of Ruxolitinib in Patients with Myelofibrosis Receiving Concomitant Potent CYP3A4 Inhibitors or Fluconazole
Baseline Platelet Count Recommended Initial Ruxolitinib Dosage >=100,000/mm3 10 mg twice daily 50,000 to <100,000/mm3 5 mg twice daily
If a stable dosage of ruxolitinib has been achieved in patients with myelofibrosis receiving concomitant potent CYP3A4 inhibitors or fluconazole at a dosage of <=200 mg daily, the dosage of ruxolitinib should be reduced as described in Table 5.
Table 5. Recommended Dosage Modification of Ruxolitinib in Patients with Myelofibrosis Receiving Concomitant Potent CYP3A4 Inhibitors or Fluconazole
Current Stable Dosage of Ruxolitinib Recommended Ruxolitinib Dosage Modification >=10 mg twice daily Decrease ruxolitinib dosage by 50% (round up to the next available tablet strength) 5 mg twice daily 5 mg once daily 5 mg once daily Avoid potent CYP3A4 inhibitor or fluconazole therapy or temporarily withhold ruxolitinib therapy for the duration of CYP3A4 inhibitor or fluconazole use
Dosage reduction should be considered for hemoglobin concentration <12 g/dL or platelet count <100,000/mm3 to avoid interruption of therapy (see Table 6).
Table 6. Dosage Reduction For Hematologic Parameters in Patients with Polycythemia Vera
Hemoglobin and/or Platelet Count Recommended Ruxolitinib Dosage Reduction Hemoglobin >=12 g/dL AND platelet No dosage adjustment count >=100,000/mm3 Hemoglobin 10 to <12 g/dL AND Consider reducing the dosage to platelet count 75,000 to avoid interruption of therapy <100,000/mm3 Hemoglobin 8 to <10 g/dL OR platelet Reduce dosage by 5 mg twice daily count 50,000 to <75,000/mm3 For patients currently receiving 5 mg twice daily, decrease ruxolitinib dosage to 5 mg once daily
If hemoglobin <8 g/dL, platelet count <50,000/mm3, or ANC <1000/mm3 occurs, ruxolitinib should be withheld until hematologic parameters recover to acceptable levels; ruxolitinib therapy may then be resumed at a reduced dosage as described in Table 7.
Table 7. Maximum Recommended Dosage of Ruxolitinib Following Interruption of Therapy for Hematologic Parameters in Patients with Polycythemia Vera
Hematologic Parameters Maximum Recommended Dosage Following Interruption of Therapy Hemoglobin 8 to <10 g/dL OR platelet Resume at maximum dosage of 5 mg count 50,000 to <75,000/mm3 OR ANC twice daily or no more than 5 mg 1000 to <1500/mm3 twice daily less than the dose that resulted in dosage interruption Hemoglobin 10 to <12 g/dL OR Resume at maximum dosage of 10 mg platelet count 75,000 to twice daily or no more than 5 mg <100,000/mm3 OR ANC 1500 to twice daily less than the dose that <2000/mm3 resulted in dosage interruption Hemoglobin >=12 g/dL OR platelet Resume at maximum dosage of 15 mg count >=100,000/mm3 OR ANC twice daily or no more than 5 mg >=2000/mm3 twice daily less than the dose that resulted in dosage interruption
The most severe hematologic parameter should be used to determine the corresponding maximum dosage.
Continue therapy for at least 2 weeks; if stable, the dosage of ruxolitinib may be increased by 5 mg twice daily.
If dosage interruption is necessary on a reduced dosage of 5 mg twice daily, ruxolitinib may be resumed at a dosage of 5 mg twice daily or 5 mg once daily, but not higher, once hemoglobin concentration improves to >=10 g/dL, platelet count improves to >=75,000/mm3, and ANC improves to >=1500/mm3.
The dosage of ruxolitinib may be titrated following treatment interruption; however, the maximum total daily dosage should not exceed 5 mg less than the dosage that resulted in the dosage interruption. The manufacturer states that the maximal total daily dosage of ruxolitinib is not limited in patients who required treatment interruption following phlebotomy-associated anemia.
If clinical response is considered insufficient and platelet, hemoglobin, and neutrophil counts are adequate, the dosage of ruxolitinib may be increased in increments of 5 mg twice daily up to a maximum of 25 mg twice daily if all the following conditions have been met: inadequate efficacy (demonstrated by one or more of the following: continued need for phlebotomy, white blood cell (WBC) or platelet count above the upper limit of normal (ULN), or spleen size that is reduced by <25% in palpable length from baseline); platelet count >=140,000/mm3; hemoglobin concentration >=12 g/dL; ANC >=1500/mm3.
Do not increase the ruxolitinib dosage during the first 4 weeks of therapy or more frequently than every 2 weeks.
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. The initial dosage of ruxolitinib should be reduced to 5 mg twice daily. Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
If a stable dosage of ruxolitinib has been achieved in patients with polycythemia vera receiving concomitant potent CYP3A4 inhibitors of fluconazole at a dosage of <=200 mg daily, the dosage of ruxolitinib should be reduced as described in Table 8.
Table 8. Recommended Dosage Modification of Ruxolitinib in Patients with Polycythemia Vera Receiving Concomitant Potent CYP3A4 Inhibitors or Fluconazole
Current Stable Dosage of Ruxolitinib Recommended Ruxolitinib Dosage Modification >=10 mg twice daily Decrease ruxolitinib dosage by 50% (round up to the next available tablet strength) 5 mg twice daily 5 mg once daily 5 mg once daily Avoid potent CYP3A4 inhibitor or fluconazole therapy or temporarily withhold ruxolitinib therapy for the duration of CYP3A4 inhibitor or fluconazole use
If adverse reactions occur during ruxolitinib therapy, temporary interruption of therapy and/or dosage reduction of the drug may be necessary. If dosage reduction is required, reduce dosage as described in Table 9.
Table 9. Recommended Dosage Reduction for Ruxolitinib Toxicity in Patients with Acute GVHD
Current Ruxolitinib Dosage Recommended Dosage Reduction 10 mg twice daily Reduce dosage to 5 mg twice daily 5 mg twice daily Reduce dosage to 5 mg once daily 5 mg once daily Interrupt therapy until clinical and/or laboratory parameters recover
If an adverse reaction occurs, modify dosage accordingly (see Table 10).
Table 10. Recommended Dosage Modification for Ruxolitinib Toxicity in Patients with Acute GVHD
Laboratory Parameter Recommended Dosage Modification Clinically significant Reduce ruxolitinib dosage by 1 dose thrombocytopenia despite supportive level; when platelet count recovers measures to previous values, return dosage to previous dosage ANC <1000/mm3 considered related to Temporarily interrupt therapy for up ruxolitinib therapy to 14 days, then resume ruxolitinib at a dosage reduced by 1 dose level Total bilirubin concentration 3-5 Reduce ruxolitinib dosage by 1 dose times the ULN in patients without level until recovery of total liver GVHD bilirubin concentrations Total bilirubin concentration >5 to Temporarily withhold ruxolitinib 10 times the ULN in patients without therapy for up to 14 days until liver GVHD total bilirubin concentrations improve to <=1.5 times the ULN, then resume ruxolitinib at same dosage Total bilirubin concentration >10 Temporarily withhold ruxolitinib times the ULN in patients without therapy for up to 14 days until liver GVHD total bilirubin concentration improves to <=1.5 times the ULN, then resume ruxolitinib at a dosage reduced by 1 dose level Total bilirubin concentration >3 Reduce ruxolitinib dosage by 1 dose times the ULN in patients with liver level until recovery of total GVHD bilirubin concentrations
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
If coadministration with fluconazole at dosages of up to 200 mg per day is necessary in patients with acute GVHD, reduce the starting dosage of ruxolitinib to 5 mg once daily.
If coadministration with a potent CYP3A4 inhibitor (other than fluconazole) is necessary in patients with acute GVHD, monitor CBCs more frequently and adjust ruxolitinib dosage for adverse effects, if necessary.
If adverse reactions occur during ruxolitinib therapy, temporary interruption of therapy and/or dosage reduction of the drug may be necessary. If dosage reduction is required, reduce dosage as described in Table 11.
Table 11. Recommended Dosage Reduction for Ruxolitinib Toxicity in Patients with Chronic GVHD
Current Ruxolitinib Dosage Recommended Dosage Reduction 10 mg twice daily Reduce dosage to 5 mg twice daily 5 mg twice daily Reduce dosage to 5 mg once daily 5 mg once daily Interrupt therapy until clinical and/or laboratory parameters recover
If an adverse reaction occurs, modify dosage accordingly (see Table 12).
Table 12. Recommended Dosage Modification for Ruxolitinib Toxicity in Patients with Chronic GVHD
Laboratory Parameter Recommended Dosage Modification Platelet count <20,000/mm3 Continue ruxolitinib at a dosage reduced by 1 dose level If thrombocytopenia resolves within 7 days, return dosage to initial dosage If thrombocytopenia does not resolve within 7 days, maintain the reduced dosage of ruxolitinib ANC <750/mm3 considered related to Continue ruxolitinib at a dosage ruxolitinib therapy reduced by 1 dose level; when neutropenia resolves, dosage may be returned to initial dosage ANC <500/mm3 considered related to Temporarily withhold ruxolitinib ruxolitinib therapy therapy for up to 14 days until neutropenia resolves, then resume ruxolitinib at a dosage reduced by 1 dose level When ANC improves to >1000/mm3, may return to initial dosage level Total bilirubin concentration 3-5 Continue ruxolitinib at a dosage times the ULN reduced by 1 dose level until elevated total bilirubin concentrations resolve If elevated total bilirubin concentrations resolve within 14 days, increase the dosage by 1 dose level If elevated total bilirubin concentrations do not resolve within 14 days, maintain the reduced dosage of ruxolitinib Total bilirubin concentration >5 to Temporarily withhold ruxolitinib 10 times the ULN therapy for up to 14 days until elevated total bilirubin concentrations resolve, then resume ruxolitinib at same dosage If elevated total bilirubin concentrations do not resolve within 14 days, resume ruxolitinib at a dosage reduced by 1 dose level upon recovery Total bilirubin concentration >10 Temporarily withhold ruxolitinib times the ULN therapy for up to 14 days until elevated total bilirubin concentrations resolve, then resume ruxolitinib at a dosage reduced by 1 dose level If elevated total bilirubin concentrations do not resolve within 14 days, discontinue drug Other toxicity of grade 3 severity Reduce ruxolitinib dosage by 1 dose level until toxicity resolves Other toxicity of grade 4 severity Discontinue drug
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
If coadministration with fluconazole at dosages of up to 200 mg per day is necessary in patients with chronic GVHD, reduce the starting dosage of ruxolitinib to 5 mg twice daily.
If coadministration with a potent CYP3A4 inhibitor (other than fluconazole) is necessary in patients with chronic GVHD, CBCs should be monitored more frequently for toxicity and the dosage of ruxolitinib should be modified for adverse effects, if they occur.
Dosage reductions may be considered based on platelet count without interrupting therapy in patients with a baseline platelet count >=100,000/mm3(see Table 1) and in patients with a baseline platelet count of 50,000 to <100,000/mm3(see Table 2). However, temporary interruption of therapy is necessary in patients with a baseline platelet count of >=100,000/mm3 if platelet count decreases to <50,000/mm3 or ANC decreases to <500/mm3.
Table 1. Recommended Dosage Reduction for Platelet Count in Patients with Baseline Platelet Count >=100,000/mm3
Current Platelet Count and Recommended Ruxolitinib Dosage Ruxolitinib Dosage 100,000 to <125,000/mm3 on a 20 mg twice daily ruxolitinib dosage of 25 mg twice daily 100,000 to <125,000/mm3 on a 15 mg twice daily ruxolitinib dosage of 20 mg twice daily 100,000 to <125,000/mm3 on a No dosage adjustment ruxolitinib dosage of 5, 10, or 15 mg twice daily 75,000 to <100,000/mm3 on a 10 mg twice daily ruxolitinib dosage of 15, 20, or 25 mg twice daily 75,000 to <100,000/mm3 on a No dosage adjustment ruxolitinib dosage of 5 or 10 mg twice daily 50,000 to <75,000/mm3 on a 5 mg twice daily ruxolitinib dosage of 10, 15, 20, or 25 mg twice daily 50,000 to <75,000/mm3 on a No dosage adjustment ruxolitinib dosage of 5 mg twice daily
Table 2. Recommended Dosage Reduction for Platelet Count in Patients with Baseline Platelet Count 50,000 to <100,000/mm3
Current Platelet Count Recommended Ruxolitinib Dosage Reduction 25,000 to <35,000/mm3 AND decline in Reduce ruxolitinib dosage by 5 mg platelet count is <20% during the once daily prior 4 weeks For patients currently receiving 5 mg once daily, maintain dosage 25,000 to <35,000/mm3 AND decline in Reduce dosage by 5 mg twice daily platelet count is >=20% during the prior 4 weeks For patients currently receiving 5 mg twice daily, decrease dosage to 5 mg once daily For patients receiving 5 mg once daily, maintain dosage
In patients with a baseline platelet count of >=100,000/mm3, temporarily interrupt ruxolitinib therapy if platelet count decreases to <50,000/mm3 or ANC decreases to <500/mm3. When platelet counts improve to >50,000/mm3 and ANC improves to >750/mm3, ruxolitinib may be resumed. When restarting, begin with a dosage at least 5 mg twice daily below the dosage at interruption and follow the manufacturer's guidelines for the maximum allowable dosage that may be used when restarting treatment (see Table 3).
Table 3. Maximum Restarting Dosage of Ruxolitinib Following Interruption of Therapy for Thrombocytopenia in Patients with Baseline Platelet Count >=100,000/mm3
Current Platelet Count Maximum Recommended Dosage Following Interruption of Therapy >=125,000/mm3 Maximum dosage of 20 mg twice daily 100,000 to <125,000/mm3 Maximum dosage of 15 mg twice daily 75,000 to <100,000/mm3 Maximum dosage of 10 mg twice daily for at least 2 weeks; if stable, may increase to 15 mg twice daily 50,000 to <75,000/mm3 Maximum dosage of 5 mg twice daily for at least 2 weeks; if stable, may increase to 10 mg twice daily <50,000/mm3 Continue to withhold therapy
If ANC <500/mm3 occurs, temporarily interrupt ruxolitinib therapy; when ANC improves to >=750/mm3, ruxolitinib may be resumed at the higher of the following dosages: 5 mg once daily; or 5 mg twice daily below the highest dosage in the week prior to the treatment interruption.
In patients with a baseline platelet count of 50,000/mm3 to <100,000/mm3, temporarily interrupt ruxolitinib therapy if platelet count decreases to <25,000/mm3 or ANC decreases to <500/mm3. When platelet counts improve to >35,000/mm3 and ANC improves to >750/mm3, ruxolitinib may be resumed at the higher of the following dosages: 5 mg once daily; or 5 mg twice daily below the highest dosage during the week prior to the treatment interruption.
If clinical response is considered insufficient in patients with a baseline platelet count of >=100,000/mm3, the dosage of ruxolitinib may be increased in increments of 5 mg twice daily up to a maximum of 25 mg twice daily if all the following conditions have been met: failure to achieve a reduction from pretreatment baseline spleen size of either 50% in palpable length or 35% in volume as measured by CT or MRI; platelet count >125,000/mm3 at 4 weeks; platelet count never reduced to <100,000/mm3; ANC >750/mm3.
Based on limited clinical data, long-term maintenance with ruxolitinib at a dosage of 5 mg twice daily has not shown response; therefore, continued long-term use of the drug at a dosage of 5 mg twice daily should be limited to patients in whom benefits outweigh the potential risks.
If clinical response is considered insufficient in patients with a baseline platelet count of 50,000/mm3 to <100,000/mm3, the dosage of ruxolitinib may be increased in increments of 5 mg daily up to a maximum of 10 mg twice daily if the following conditions have been met: platelet count has remained >=40,000/mm3 and has not decreased by more than 20% in the prior 4 weeks; ANC is >1000/mm3; and the dosage of ruxolitinib has not been reduced or withheld due to an adverse event or hematologic toxicity in the prior 4 weeks. Continuation of ruxolitinib beyond a duration of 6 months should be limited to patients in whom the benefits outweigh the potential risks.
Do not increase the ruxolitinib dosage during the first 4 weeks of therapy or more frequently than every 2 weeks.
If the size of the spleen does not reduce or symptoms do not improve following 6 months of therapy with ruxolitinib, the drug should be discontinued.
If a hemorrhagic event requiring intervention occurs during ruxolitinib therapy in patients with myelofibrosis, interrupt treatment regardless of the current platelet count. If the hemorrhagic event resolves and the underlying cause of bleeding is controlled, consider resuming ruxolitinib at the dosage used prior to treatment interruption. If the hemorrhagic event resolves but the underlying cause persists, consider resuming ruxolitinib at a reduced dosage.
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. The initial dosage of ruxolitinib should be reduced based on baseline platelet count. (See Table 4.) Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
Table 4. Recommended Initial Dosage of Ruxolitinib in Patients with Myelofibrosis Receiving Concomitant Potent CYP3A4 Inhibitors or Fluconazole
Baseline Platelet Count Recommended Initial Ruxolitinib Dosage >=100,000/mm3 10 mg twice daily 50,000 to <100,000/mm3 5 mg twice daily
If a stable dosage of ruxolitinib has been achieved in patients with myelofibrosis receiving concomitant potent CYP3A4 inhibitors or fluconazole at a dosage of <=200 mg daily, the dosage of ruxolitinib should be reduced as described in Table 5.
Table 5. Recommended Dosage Modification of Ruxolitinib in Patients with Myelofibrosis Receiving Concomitant Potent CYP3A4 Inhibitors or Fluconazole
Current Stable Dosage of Ruxolitinib Recommended Ruxolitinib Dosage Modification >=10 mg twice daily Decrease ruxolitinib dosage by 50% (round up to the next available tablet strength) 5 mg twice daily 5 mg once daily 5 mg once daily Avoid potent CYP3A4 inhibitor or fluconazole therapy or temporarily withhold ruxolitinib therapy for the duration of CYP3A4 inhibitor or fluconazole use
Dosage reduction should be considered for hemoglobin concentration <12 g/dL or platelet count <100,000/mm3 to avoid interruption of therapy (see Table 6).
Table 6. Dosage Reduction For Hematologic Parameters in Patients with Polycythemia Vera
Hemoglobin and/or Platelet Count Recommended Ruxolitinib Dosage Reduction Hemoglobin >=12 g/dL AND platelet No dosage adjustment count >=100,000/mm3 Hemoglobin 10 to <12 g/dL AND Consider reducing the dosage to platelet count 75,000 to avoid interruption of therapy <100,000/mm3 Hemoglobin 8 to <10 g/dL OR platelet Reduce dosage by 5 mg twice daily count 50,000 to <75,000/mm3 For patients currently receiving 5 mg twice daily, decrease ruxolitinib dosage to 5 mg once daily
If hemoglobin <8 g/dL, platelet count <50,000/mm3, or ANC <1000/mm3 occurs, ruxolitinib should be withheld until hematologic parameters recover to acceptable levels; ruxolitinib therapy may then be resumed at a reduced dosage as described in Table 7.
Table 7. Maximum Recommended Dosage of Ruxolitinib Following Interruption of Therapy for Hematologic Parameters in Patients with Polycythemia Vera
Hematologic Parameters Maximum Recommended Dosage Following Interruption of Therapy Hemoglobin 8 to <10 g/dL OR platelet Resume at maximum dosage of 5 mg count 50,000 to <75,000/mm3 OR ANC twice daily or no more than 5 mg 1000 to <1500/mm3 twice daily less than the dose that resulted in dosage interruption Hemoglobin 10 to <12 g/dL OR Resume at maximum dosage of 10 mg platelet count 75,000 to twice daily or no more than 5 mg <100,000/mm3 OR ANC 1500 to twice daily less than the dose that <2000/mm3 resulted in dosage interruption Hemoglobin >=12 g/dL OR platelet Resume at maximum dosage of 15 mg count >=100,000/mm3 OR ANC twice daily or no more than 5 mg >=2000/mm3 twice daily less than the dose that resulted in dosage interruption
The most severe hematologic parameter should be used to determine the corresponding maximum dosage.
Continue therapy for at least 2 weeks; if stable, the dosage of ruxolitinib may be increased by 5 mg twice daily.
If dosage interruption is necessary on a reduced dosage of 5 mg twice daily, ruxolitinib may be resumed at a dosage of 5 mg twice daily or 5 mg once daily, but not higher, once hemoglobin concentration improves to >=10 g/dL, platelet count improves to >=75,000/mm3, and ANC improves to >=1500/mm3.
The dosage of ruxolitinib may be titrated following treatment interruption; however, the maximum total daily dosage should not exceed 5 mg less than the dosage that resulted in the dosage interruption. The manufacturer states that the maximal total daily dosage of ruxolitinib is not limited in patients who required treatment interruption following phlebotomy-associated anemia.
If clinical response is considered insufficient and platelet, hemoglobin, and neutrophil counts are adequate, the dosage of ruxolitinib may be increased in increments of 5 mg twice daily up to a maximum of 25 mg twice daily if all the following conditions have been met: inadequate efficacy (demonstrated by one or more of the following: continued need for phlebotomy, white blood cell (WBC) or platelet count above the upper limit of normal (ULN), or spleen size that is reduced by <25% in palpable length from baseline); platelet count >=140,000/mm3; hemoglobin concentration >=12 g/dL; ANC >=1500/mm3.
Do not increase the ruxolitinib dosage during the first 4 weeks of therapy or more frequently than every 2 weeks.
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. The initial dosage of ruxolitinib should be reduced to 5 mg twice daily. Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
If a stable dosage of ruxolitinib has been achieved in patients with polycythemia vera receiving concomitant potent CYP3A4 inhibitors of fluconazole at a dosage of <=200 mg daily, the dosage of ruxolitinib should be reduced as described in Table 8.
Table 8. Recommended Dosage Modification of Ruxolitinib in Patients with Polycythemia Vera Receiving Concomitant Potent CYP3A4 Inhibitors or Fluconazole
Current Stable Dosage of Ruxolitinib Recommended Ruxolitinib Dosage Modification >=10 mg twice daily Decrease ruxolitinib dosage by 50% (round up to the next available tablet strength) 5 mg twice daily 5 mg once daily 5 mg once daily Avoid potent CYP3A4 inhibitor or fluconazole therapy or temporarily withhold ruxolitinib therapy for the duration of CYP3A4 inhibitor or fluconazole use
If adverse reactions occur during ruxolitinib therapy, temporary interruption of therapy and/or dosage reduction of the drug may be necessary. If dosage reduction is required, reduce dosage as described in Table 9.
Table 9. Recommended Dosage Reduction for Ruxolitinib Toxicity in Patients with Acute GVHD
Current Ruxolitinib Dosage Recommended Dosage Reduction 10 mg twice daily Reduce dosage to 5 mg twice daily 5 mg twice daily Reduce dosage to 5 mg once daily 5 mg once daily Interrupt therapy until clinical and/or laboratory parameters recover
If an adverse reaction occurs, modify dosage accordingly (see Table 10).
Table 10. Recommended Dosage Modification for Ruxolitinib Toxicity in Patients with Acute GVHD
Laboratory Parameter Recommended Dosage Modification Clinically significant Reduce ruxolitinib dosage by 1 dose thrombocytopenia despite supportive level; when platelet count recovers measures to previous values, return dosage to previous dosage ANC <1000/mm3 considered related to Temporarily interrupt therapy for up ruxolitinib therapy to 14 days, then resume ruxolitinib at a dosage reduced by 1 dose level Total bilirubin concentration 3-5 Reduce ruxolitinib dosage by 1 dose times the ULN in patients without level until recovery of total liver GVHD bilirubin concentrations Total bilirubin concentration >5 to Temporarily withhold ruxolitinib 10 times the ULN in patients without therapy for up to 14 days until liver GVHD total bilirubin concentrations improve to <=1.5 times the ULN, then resume ruxolitinib at same dosage Total bilirubin concentration >10 Temporarily withhold ruxolitinib times the ULN in patients without therapy for up to 14 days until liver GVHD total bilirubin concentration improves to <=1.5 times the ULN, then resume ruxolitinib at a dosage reduced by 1 dose level Total bilirubin concentration >3 Reduce ruxolitinib dosage by 1 dose times the ULN in patients with liver level until recovery of total GVHD bilirubin concentrations
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
If coadministration with fluconazole at dosages of up to 200 mg per day is necessary in patients with acute GVHD, reduce the starting dosage of ruxolitinib to 5 mg once daily.
If coadministration with a potent CYP3A4 inhibitor (other than fluconazole) is necessary in patients with acute GVHD, monitor CBCs more frequently and adjust ruxolitinib dosage for adverse effects, if necessary.
If adverse reactions occur during ruxolitinib therapy, temporary interruption of therapy and/or dosage reduction of the drug may be necessary. If dosage reduction is required, reduce dosage as described in Table 11.
Table 11. Recommended Dosage Reduction for Ruxolitinib Toxicity in Patients with Chronic GVHD
Current Ruxolitinib Dosage Recommended Dosage Reduction 10 mg twice daily Reduce dosage to 5 mg twice daily 5 mg twice daily Reduce dosage to 5 mg once daily 5 mg once daily Interrupt therapy until clinical and/or laboratory parameters recover
If an adverse reaction occurs, modify dosage accordingly (see Table 12).
Table 12. Recommended Dosage Modification for Ruxolitinib Toxicity in Patients with Chronic GVHD
Laboratory Parameter Recommended Dosage Modification Platelet count <20,000/mm3 Continue ruxolitinib at a dosage reduced by 1 dose level If thrombocytopenia resolves within 7 days, return dosage to initial dosage If thrombocytopenia does not resolve within 7 days, maintain the reduced dosage of ruxolitinib ANC <750/mm3 considered related to Continue ruxolitinib at a dosage ruxolitinib therapy reduced by 1 dose level; when neutropenia resolves, dosage may be returned to initial dosage ANC <500/mm3 considered related to Temporarily withhold ruxolitinib ruxolitinib therapy therapy for up to 14 days until neutropenia resolves, then resume ruxolitinib at a dosage reduced by 1 dose level When ANC improves to >1000/mm3, may return to initial dosage level Total bilirubin concentration 3-5 Continue ruxolitinib at a dosage times the ULN reduced by 1 dose level until elevated total bilirubin concentrations resolve If elevated total bilirubin concentrations resolve within 14 days, increase the dosage by 1 dose level If elevated total bilirubin concentrations do not resolve within 14 days, maintain the reduced dosage of ruxolitinib Total bilirubin concentration >5 to Temporarily withhold ruxolitinib 10 times the ULN therapy for up to 14 days until elevated total bilirubin concentrations resolve, then resume ruxolitinib at same dosage If elevated total bilirubin concentrations do not resolve within 14 days, resume ruxolitinib at a dosage reduced by 1 dose level upon recovery Total bilirubin concentration >10 Temporarily withhold ruxolitinib times the ULN therapy for up to 14 days until elevated total bilirubin concentrations resolve, then resume ruxolitinib at a dosage reduced by 1 dose level If elevated total bilirubin concentrations do not resolve within 14 days, discontinue drug Other toxicity of grade 3 severity Reduce ruxolitinib dosage by 1 dose level until toxicity resolves Other toxicity of grade 4 severity Discontinue drug
Dosage adjustment is recommended in patients receiving concomitant ruxolitinib with a potent inhibitor of cytochrome P-450 (CYP) isoenzyme 3A4 or fluconazole at dosage of <=200 mg daily. Avoid concomitant use of ruxolitinib with fluconazole at a dosage >200 mg daily.
If coadministration with fluconazole at dosages of up to 200 mg per day is necessary in patients with chronic GVHD, reduce the starting dosage of ruxolitinib to 5 mg twice daily.
If coadministration with a potent CYP3A4 inhibitor (other than fluconazole) is necessary in patients with chronic GVHD, CBCs should be monitored more frequently for toxicity and the dosage of ruxolitinib should be modified for adverse effects, if they occur.
Ruxolitinib is administered orally and can be taken with or without food. If a dose is missed, the patient should not take an additional dose, but should take the next scheduled dose. For patients unable to swallow tablets, a ruxolitinib tablet can be dispersed in a glass of water containing approximately 40 mL and administered through a nasogastric tube (8 French or larger).
The water should be stirred for approximately 10 minutes; once the tablet has dispersed, the suspension should be administered within 6 hours through a nasogastric tube using an appropriate syringe. Following administration, the tube should be rinsed with approximately 75 mL of water. Store ruxolitinib at room temperature (20-25degreesC). Excursions are permitted between 15-30oC.
The water should be stirred for approximately 10 minutes; once the tablet has dispersed, the suspension should be administered within 6 hours through a nasogastric tube using an appropriate syringe. Following administration, the tube should be rinsed with approximately 75 mL of water. Store ruxolitinib at room temperature (20-25degreesC). Excursions are permitted between 15-30oC.
| DRUG LABEL | DOSING TYPE | DOSING INSTRUCTIONS |
|---|---|---|
| JAKAFI 5 MG TABLET | Maintenance | Adults take 1 tablet (5 mg) by oral route 2 times per day |
| JAKAFI 10 MG TABLET | Maintenance | Adults take 1 tablet (10 mg) by oral route 2 times per day |
| JAKAFI 15 MG TABLET | Maintenance | Adults take 1 tablet (15 mg) by oral route 2 times per day |
| JAKAFI 20 MG TABLET | Maintenance | Adults take 1 tablet (20 mg) by oral route 2 times per day |
| JAKAFI 25 MG TABLET | Maintenance | Adults take 1 tablet (25 mg) by oral route 2 times per day |
No generic dosing information available.
The following drug interaction information is available for JAKAFI (ruxolitinib phosphate):
There are 5 contraindications.
These drug combinations generally should not be dispensed or administered to the same patient. A manufacturer label warning that indicates the contraindication warrants inclusion of a drug combination in this category, regardless of clinical evidence or lack of clinical evidence to support the contraindication.
| Drug Interaction | Drug Names |
|---|---|
| Efalizumab; Natalizumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: Natalizumab,(1-3) efalizumab,(4) immunosuppressives, and immunomodulators all suppress the immune system. CLINICAL EFFECTS: Concurrent use of natalizumab(1-3) or efalizumab(4) with immunosuppressives or immunomodulators may result in an increased risk of infections, including progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV). PREDISPOSING FACTORS: Previous JCV infection, longer duration of natalizumab treatment - especially if greater than 2 years, and prior or concomitant treatment with immunosuppressant medication are all independent risk factors which increase the risk for PML.(1,5) The FDA has estimated PML incidence stratified by risk factors: If anti-JCV antibody positive, no prior immunosuppressant use and natalizumab treatment less than 25 months, incidence <1/1,000. If anti-JCV antibody positive, history of prior immunosuppressant use and natalizumab treatment less than 25 months, incidence 2/1,000 If anti-JCV antibody positive, no prior immunosuppressant use and natalizumab treatment 25-48 months, incidence 4/1,000 If anti-JCV antibody positive, history of prior immunosuppressant use and natalizumab treatment 25-48 months, incidence 11/1,000. PATIENT MANAGEMENT: The US manufacturer of natalizumab states patients with Crohn's disease should not receive concurrent immunosuppressants, with the exception of limited overlap of corticosteroids, due to the increased risk for PML. For new natalizumab patients currently receiving chronic oral corticosteroids for Crohn's Disease, begin corticosteroid taper when therapeutic response to natalizumab has occurred. If corticosteroids cannot be discontinued within six months of starting natalizumab, discontinue natalizumab.(3) The US manufacturer of natalizumab states that natalizumab should not ordinarily be used in multiple sclerosis patients receiving immunosuppressants or immunomodulators due to the increased risk for PML. Immunosuppressives include, but are not limited to azathioprine, cyclophosphamide, cyclosporine, mercaptopurine, methotrexate, mitoxantrone, mycophenolate, and corticosteroids.(3,6) The UK manufacturer of natalizumab states that concurrent use with immunosuppressives or antineoplastic agents is contraindicated.(1) The Canadian manufacturer of natalizumab states that natalizumab should not be used with immunosuppressive or immunomodulatory agents.(2) The US manufacturer of certolizumab states that concurrent therapy with natalizumab is not recommended.(7) DISCUSSION: Progressive multifocal leukoencephalopathy has been reported in patients receiving concurrent natalizumab were recently or concomitantly taking immunomodulators or immunosuppressants.(1-5,8,9) In a retrospective cohort study of multiple sclerosis patients newly initiated on a disease-modifying therapy, use of high-efficacy agents (alemtuzumab, natalizumab, or ocrelizumab) resulted in the same risk of overall infections as moderate-efficacy agents, but there was an elevated risk of serious infections (adjusted hazard ratio [aHR] = 1.24, 95% confidence interval (CI) = 1.06-1.44) and UTIs (aHR = 1.21, 95% CI = 1.14-1.30).(10) |
TYRUKO, TYSABRI |
| Live Vaccines; Live BCG/Selected Immunosuppressive Agents SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: A variety of disease modifying agents suppress the immune system. Immunocompromised patients may be at increased risk for uninhibited replication after administration of live, attenuated vaccines or intravesicular BCG. Immune response to vaccines may be decreased during periods of immunocompromise.(1) CLINICAL EFFECTS: The expected serum antibody response may not be obtained and/or the vaccine may result in illness.(1) After instillation of intravesicular BCG, immunosuppression may interfere with local immune response, or increase the severity of mycobacterial infection following inadvertent systemic exposure.(2) PREDISPOSING FACTORS: Immunosuppressive diseases (e.g. hematologic malignancies, HIV disease), treatments (e.g. radiation) and drugs may all increase the magnitude of immunodeficiency. PATIENT MANAGEMENT: The Centers for Disease Control(CDC) Advisory Committee on Immunization Practices (ACIP) states that live-virus and live, attenuated vaccines should not be administered to patients who are immunocompromised. The magnitude of immunocompromise and associated risks should be determined by a physician.(1) For patients scheduled to receive chemotherapy, vaccination should ideally precede the initiation of chemotherapy by 14 days. Patients vaccinated while on immunosuppressive therapy or in the 2 weeks prior to starting therapy should be considered unimmunized and should be revaccinated at least 3 months after discontinuation of therapy.(1) Patients who receive anti-B cell therapies should not receive live vaccines for at least 6 months after such therapies due to a prolonged duration of immunosuppression. An exception is the Zoster vaccine, which can be given at least 1 month after receipt of anti-B cell therapies.(1) The US manufacturer of abatacept states live vaccines should not be given during or for up to 3 months after discontinuation of abatacept.(2) The US manufacturer of live BCG for intravesicular treatment of bladder cancer states use is contraindicated in immunosuppressed patients.(3) The US manufacturer of daclizumab states live vaccines are not recommended during and for up to 4 months after discontinuation of treatment.(4) The US manufacturer of guselkumab states that live vaccines should be avoided during treatment with guselkumab.(5) The US manufacturer of inebilizumab-cdon states that live vaccines are not recommended during treatment and after discontinuation until B-cell repletion. Administer all live vaccinations at least 4 weeks prior to initiation of inebilizumab-cdon.(6) The US manufacturer of ocrelizumab states that live vaccines are not recommended during treatment and until B-cell repletion occurs after discontinuation of therapy. Administer all live vaccines at least 4 weeks prior to initiation of ocrelizumab.(7) The US manufacturer of ozanimod states that live vaccines should be avoided during and for up to 3 months after discontinuation of ozanimod.(8) The US manufacturer of siponimod states that live vaccines are not recommended during treatment and for up to 4 weeks after discontinuation of treatment.(9) The US manufacturer of ustekinumab states BCG vaccines should not be given in the year prior to, during, or the year after ustekinumab therapy.(10) The US manufacturer of satralizumab-mwge states that live vaccines are not recommended during treatment and should be administered at least four weeks prior to initiation of satralizumab-mwge.(11) The US manufacturer of ublituximab-xiiy states that live vaccines are not recommended during treatment and until B-cell recovery. Live vaccines should be administered at least 4 weeks prior to initiation of ublituximab-xiiy.(12) The US manufacturer of etrasimod states that live vaccines should be avoided during and for 5 weeks after treatment. Live vaccines should be administered at least 4 weeks prior to initiation of etrasimod.(13) The US manufacturer of emapalumab-lzsg states that live vaccines should not be administered to patients receiving emapalumab-lzsg and for at least 4 weeks after the last dose of emapalumab-lzsg. The safety of immunization with live vaccines during or following emapalumab-lzsg therapy has not been studied.(14) The US manufacturer of sibeprenlimab-szsi states live vaccines should not be given within 30 days prior to initiation or during treatment with sibeprenlimab-szsi.(15) DISCUSSION: Killed or inactivated vaccines do not pose a danger to immunocompromised patients.(1) Patients with a history of leukemia who are in remission and have not received chemotherapy for at least 3 months are not considered to be immunocompromised.(1) |
ACAM2000 (NATIONAL STOCKPILE), ADENOVIRUS TYPE 4, ADENOVIRUS TYPE 4 AND TYPE 7, ADENOVIRUS TYPE 7, BCG (TICE STRAIN), BCG VACCINE (TICE STRAIN), DENGVAXIA, ERVEBO (NATIONAL STOCKPILE), FLUMIST 2026-2027, FLUMIST HOME 2026-2027, M-M-R II VACCINE, PRIORIX, PROQUAD, ROTARIX, ROTATEQ, STAMARIL, VARIVAX VACCINE, VAXCHORA ACTIVE COMPONENT, VAXCHORA VACCINE, VIVOTIF, YF-VAX |
| Talimogene laherparepvec/Selected Immunosuppressants SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: Talimogene laherparepvec is a live, attenuated herpes simplex virus.(1) CLINICAL EFFECTS: Concurrent use of talimogene laherparepvec in patients receiving immunosuppressive therapy may cause a life-threatening disseminated herpetic infection.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Talimogene laherparepvec is contraindicated in immunosuppressed patients.(1) The magnitude of immunocompromise and associated risks due to immunosuppressant drugs should be determined by a physician. DISCUSSION: Concurrent use of talimogene laherparepvec in patients receiving immunosuppressive therapy may cause a life-threatening disseminated herpetic infection.(1) |
IMLYGIC |
| Nadofaragene Firadenovec/Selected Immunosuppressants SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: Nadofaragene firadenovec may contain low levels of replication-competent adenovirus.(1) CLINICAL EFFECTS: Concurrent use of nadofaragene firadenovec in patients receiving immunosuppressive therapy may cause disseminated adenovirus infection.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Individuals who are immunosuppressed or immune-deficient should not receive nadofaragene firadenovec.(1) DISCUSSION: Nadofaragene firadenovec is a non-replicating adenoviral vector-based gene therapy but may contain low levels of replication-competent adenovirus. Immunocompromised persons, including those receiving immunosuppressant therapy, may be at risk for disseminated adenovirus infection.(1) |
ADSTILADRIN |
| Ruxolitinib/Fluconazole (Greater Than 200 mg) SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: Fluconazole may inhibit the metabolism of ruxolitinib by CYP3A4 and CYP2C9.(1) CLINICAL EFFECTS: Concurrent use of fluconazole may increase levels of and effects from ruxolitinib, including thrombocytopenia, anemia, neutropenia, increased serious infection risk or lipid level elevations.(1) PREDISPOSING FACTORS: This interaction may be more severe in patients with a low platelet count.(1) PATIENT MANAGEMENT: For patients undergoing therapy with ruxolitinib for all indications, avoid the use of fluconazole at doses greater than 200 mg daily.(1) For patients taking fluconazole doses of less than or equal to 200 mg, reduce the dosage of ruxolitinib according to the indication. For myelofibrosis, starting doses of ruxolitinib therapy in patients concurrently taking less than or equal to 200 mg of fluconazole is based on platelet count: -In patients with a platelet count greater than or equal to 100 X 10x9/L who are receiving fluconazole at doses less than or equal to 200 mg, the recommended starting dose of ruxolitinib is 10 mg twice daily or ruxolitinib XR 22 mg once daily. -In patients with a platelet count greater than 50 X 10x9/L to less than 100 X 10x9/L who are receiving fluconazole at doses less than or equal to 200 mg, the recommended starting dose of ruxolitinib is 5 mg once daily. Do not use ruxolitinib XR.(1) For polycythemia vera, the starting dose of ruxolitinib in patients concurrently taking less than or equal to 200 mg of fluconazole is 5 mg twice daily or ruxolitinib XR 11 mg once daily.(1) In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 10 mg twice daily or more or on ruxolitinib XR doses of 22 mg once daily or more, and in whom fluconazole at doses less than or equal to 200 mg are initiated, reduce the dose of ruxolitinib by 50% (rounded up to the closest available tablet strength).(1) In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 5 mg twice daily in whom fluconazole at doses less than or equal to 200 mg is initiated, reduce the dose of ruxolitinib to 5 mg once daily. Do not use ruxolitinib XR.(1) In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 5 mg once daily or ruxolitinib XR doses of 11 mg once daily, avoid the use of fluconazole even at doses less than or equal to 200 mg, or interrupt ruxolitinib therapy for the duration of fluconazole treatment.(1) In patients with a diagnosis of acute graft-versus-host disease and concurrently taking less than or equal to 200 mg of fluconazole, the starting dose of ruxolitinib is 5 mg once daily. Do not use ruxolitinib XR.(1) In patients with a diagnosis of chronic graft-versus-host disease and concurrently taking less than or equal to 200 mg of fluconazole, the starting dose of ruxolitinib is 5 mg twice daily or ruxolitinib XR 11 mg once daily.(1) The dose should be adjusted based on monitoring of safety and efficacy.(1) DISCUSSION: Simulations in physiologically-based pharmacokinetic (PBPK) models predict that fluconazole doses of 100 mg daily will increase the area-under-curve (AUC) of ruxolitinib (10 mg twice daily) by 100%. PBPK models predict that fluconazole doses of 400 mg daily will increase the AUC of ruxolitinib (10 mg twice daily) by 300%.(1) |
DIFLUCAN, FLUCONAZOLE, FLUCONAZOLE-NACL |
There are 14 severe interactions.
These drug interactions can produce serious consequences in most patients. Actions required for severe interactions include, but are not limited to, discontinuing one or both agents, adjusting dosage, altering administration scheduling, and providing additional patient monitoring. Review the full interaction monograph for more information.
| Drug Interaction | Drug Names |
|---|---|
| Deferiprone/Selected Myelosuppressive Agents SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Concurrent use of deferiprone with other drugs known to be associated with neutropenia or agranulocytosis may increase the frequency or risk for severe toxicity.(1) CLINICAL EFFECTS: Concurrent use of deferiprone and myelosuppressive agents may result in severe neutropenia or agranulocytosis, which may be fatal. PREDISPOSING FACTORS: Agranulocytosis may be less common in patients receiving deferiprone for thalassemia, and more common in patients treated for other systemic iron overload conditions (e.g. myelodysplastic syndromes, sickle cell disease).(2,3) Inadequate monitoring appears to increase the risk for severe outcomes. Manufacturer post market surveillance found that in all fatal cases of agranulocytosis reported between 1999 and 2005, data on weekly white blood count (WBC) monitoring was missing. In three fatal cases, deferiprone was continued for two to seven days after the detection of neutropenia or agranulocytosis.(2) PATIENT MANAGEMENT: If possible, discontinue one of the drugs associated with risk for neutropenia or agranulocytosis. If alternative therapy is not available, documentation and adherence to the deferiprone monitoring protocol is essential. Baseline absolute neutrophil count (ANC) must be at least 1,500/uL prior to starting deferiprone. Monitor ANC weekly during therapy. If infection develops, interrupt deferiprone therapy and monitor ANC more frequently. If ANC is less than 1,500/uL but greater than 500/uL, discontinue deferiprone and any other drugs possibly associated with neutropenia. Initiate ANC and platelet counts daily until recovery (i.e. ANC at least 1,500/uL). If ANC is less than 500/uL, discontinue deferiprone, evaluate patient and hospitalize if appropriate. Do not resume deferiprone unless potential benefits outweigh potential risks.(1) DISCUSSION: Drugs linked to this monograph have an FDA Boxed Warning for risk of neutropenia, agranulocytosis, or pancytopenia, or have > 5% risk for neutropenia and/or warnings describing risk for myelosuppression in manufacturer prescribing information.(1-25) In pooled clinical studies submitted to the FDA, 6.1% of deferiprone patients met criteria for neutropenia and 1.7% of patients developed agranulocytosis.(1) The time to onset of agranulocytosis was highly variable with a range of 65 days to 9.2 years (median, 161 days).(3) |
DEFERIPRONE, DEFERIPRONE (3 TIMES A DAY), FERRIPROX, FERRIPROX (2 TIMES A DAY), FERRIPROX (3 TIMES A DAY) |
| Clozapine/Selected Myelosuppressive Agents SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Clozapine and other myelosuppressive agents may be associated with neutropenia or agranulocytosis.(2) CLINICAL EFFECTS: Moderate neutropenia, even if due to combination therapy, may require abrupt discontinuation of clozapine resulting in decompensation of the patient's psychiatric disorder (e.g. schizophrenia). The disease treated by the myelosuppressive agent may be compromised if myelosuppression requires dose reduction, delay, or discontinuation of the myelosuppressive agent. Undetected severe neutropenia or agranulocytosis may be fatal. PREDISPOSING FACTORS: Low white blood counts prior to initiation of the myelosuppressive agent may increase risk for clinically significant neutropenia. PATIENT MANAGEMENT: If a patient stabilized on clozapine therapy requires treatment with a myelosuppressive agent, the clozapine prescriber should consult with prescriber of the myelosuppressive agent (e.g. oncologist) to discuss treatment and monitoring options.(2) More frequent absolute neutrophil count (ANC) monitoring or treatment alternatives secondary to neutropenic episodes may need to be considered. The U.S. Food and Drug Administration (FDA) recommends that prescribers monitor patients' ANC according to the monitoring frequencies described in the prescribing information. Severe neutropenia remains a serious, potentially fatal risk that is greatest in the first several months of clozapine treatment. ANC monitoring can help identify neutropenia early to allow for timely intervention.(1-2) Australia, Canada, and U.K.: Clozapine is only available through a restricted distribution system which requires documentation of the ANC prior to dispensing. For most clozapine patients, clozapine treatment must be interrupted for a suspected clozapine-induced ANC < 1000 cells/microliter. For patients with benign ethnic neutropenia (BEN), treatment must be interrupted for suspected clozapine-induced neutropenia < 500 cells/microliter.(2) DISCUSSION: Concurrent use of clozapine and selected myelosuppressive agents may require more frequent ANC monitoring or consideration of treatment alternatives secondary to neutropenic episodes. Agents linked to this interaction generally have > 5% risk for neutropenia and/or warnings describing risk for myelosuppression in manufacturer prescribing information.(3-26) |
CLOZAPINE, CLOZAPINE ODT, CLOZARIL, VERSACLOZ |
| Selected Multiple Sclerosis Agents/Immunosuppressants; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ocrelizumab or ofatumumab in combination with immunosuppressives and immune-modulators all suppress the immune system.(1,2) CLINICAL EFFECTS: Concurrent use of ocrelizumab or ofatumumab with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1,2) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The ocrelizumab US prescribing information states: - Ocrelizumab and other immune-modulating or immunosuppressive therapies, (including immunosuppressant doses of corticosteroids) are expected to increase the risk of immunosuppression, and the risk of additive immune system effects must be considered if these therapies are coadministered with ocrelizumab. When switching from drugs with prolonged immune effects, such as daclizumab, fingolimod, natalizumab, teriflunomide, or mitoxantrone, the duration and mode of action of these drugs must be considered to avoid unintended additive immunosuppressive effects when initiating ocrelizumab.(1) The ofatumumab US prescribing information states: - Ofatumumab and other immunosuppressive therapies (including systemic corticosteroids) may have the potential for increased immunosuppressive effects and increase the risk of infection. When switching between therapies, the duration and mechanism of action of each therapy should be considered due to the potential for additive immunosuppressive effects. Ofatumumab for MS therapy has not been studied in combination with other MS agents that suppress the immune system.(2) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1,2) In a retrospective cohort study of multiple sclerosis patients newly initiated on a disease-modifying therapy, use of high-efficacy agents (alemtuzumab, natalizumab, or ocrelizumab) resulted in the same risk of overall infections as moderate-efficacy agents, but there was an elevated risk of serious infections (adjusted hazard ratio [aHR] = 1.24, 95% confidence interval (CI) = 1.06-1.44) and UTIs (aHR = 1.21, 95% CI = 1.14-1.30).(3) |
KESIMPTA PEN, OCREVUS, OCREVUS ZUNOVO |
| Inebilizumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Inebilizumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of inebilizumab with immunosuppressive or immunomodulating agents may result in myelosuppression including neutropenia resulting in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of inebilizumab states that the concurrent use of inebilizumab with immunosuppressive agents, including systemic corticosteroids, may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Inebilizumab has not been studied in combination with other immunosuppressants. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents. The most common infections reported by inebilizumab treated patients in the randomized and open-label clinical trial periods included urinary tract infections (20%), nasopharyngitis (13%), upper respiratory tract infections (8%), and influenza (7%). Although there been no cases of Hepatitis B virus reactivation or progressive multifocal leukoencephalopathy reported in patients taking inebilizumab, these infections have been observed in patients taking other B-cell-depleting antibodies.(1) |
UPLIZNA |
| Ponesimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ponesimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ponesimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection, cryptococcal infection, or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The ponesimod US prescribing information states ponesimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Caution should be used during concomitant administration because of the risk of additive immune effects during therapy and in the weeks following administration. When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects. Initiating treatment with ponesimod after alemtuzumab is not recommended. However, ponesimod can generally be started immediately after discontinuation of beta interferon or glatiramer acetate.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections, cryptococcal meningitis, disseminated cryptococcal infections, and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1) |
PONVORY |
| Sodium Iodide I 131/Myelosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Sodium iodide I 131 can cause depression of the hematopoetic system. Myelosuppressives and immunomodulators also suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of sodium iodide I 131 with agents that cause bone marrow depression, including myelosuppressives or immunomodulators, may result in an enhanced risk of hematologic disorders, including anemia, blood dyscrasias, bone marrow depression, leukopenia, and thrombocytopenia. Bone marrow depression may increase the risk of serious infections and bleeding.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of sodium iodide I 131 states that concurrent use with bone marrow depressants may enhance the depression of the hematopoetic system caused by large doses of sodium iodide I 131.(1) Sodium iodide I 131 causes a dose-dependent bone marrow suppression, including neutropenia or thrombocytopenia, in the 3 to 5 weeks following administration. Patients may be at increased risk of infections or bleeding during this time. Monitor complete blood counts within one month of therapy. If results indicate leukopenia or thrombocytopenia, dosimetry should be used to determine a safe sodium iodide I 131 activity.(1) DISCUSSION: Hematologic disorders including death have been reported with sodium iodide I 131. The most common hematologic disorders reported include anemia, blood dyscrasias, bone marrow depression, leukopenia, and thrombocytopenia.(1) |
HICON, SODIUM IODIDE I-131 |
| Fingolimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Fingolimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1-3) CLINICAL EFFECTS: Concurrent use of fingolimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1-3) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: Recommendations for fingolimod regarding this interaction differ between regulatory approving agencies. The fingolimod US prescribing information states: - Antineoplastic, immune-modulating, or immunosuppressive therapies, (including corticosteroids) are expected to increase the risk of immunosuppression, and the risk of additive immune system effects must be considered if these therapies are coadministered with fingolimod. When switching from drugs with prolonged immune effects, such as natalizumab, teriflunomide or mitoxantrone, the duration and mode of action of these drugs must be considered to avoid unintended additive immunosuppressive effects when initiating fingolimod.(1) The fingolimod Canadian prescribing information states: - Concurrent use with immunosuppressive or immunomodulatory agents is contraindicated due to the risk of additive immune system effects. However, co-administration of a short course of corticosteroids (up to 5 days) did not increase the overall rate of infection in patients participating Phase III clinical trials.(2) The fingolimod UK specific product characteristics states: - Fingolimod is contraindicated in patients currently receiving immunosuppressive therapies or those immunocompromised by prior therapies. When switching patients from another disease modifying therapy to Gilenya, the half-life and mode of action of the other therapy must be considered in order to avoid an additive immune effect whilst at the same time minimizing the risk of disease activation.(3) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1-3) |
FINGOLIMOD, GILENYA, TASCENSO ODT |
| Ozanimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ozanimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ozanimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The ozanimod US prescribing information state this information regarding this interaction: -Ozanimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Caution should be used during concomitant administration because of the risk of additive immune effects during therapy and in the week following administration. When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects. Initiating treatment with ozanimod after alemtuzumab is not recommended. However, ozanimod can generally be started immediately after discontinuation of beta interferon or glatiramer acetate.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1) |
ZEPOSIA |
| Siponimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Siponimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of siponimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The siponimod US prescribing information state this information regarding this interaction: -Siponimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Caution should be used during concomitant administration because of the risk of additive immune effects during therapy and in the week following administration. When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects. Initiating treatment with siponimod after alemtuzumab is not recommended. However, siponimod can generally be started immediately after discontinuation of beta interferon or glatiramer acetate.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1) |
MAYZENT |
| Cladribine Oral/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Cladribine in combination with immunosuppressives and immune-modulators all suppress the immune system.(1-2) CLINICAL EFFECTS: Concurrent use of cladribine with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1-2) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: Recommendations for cladribine regarding this interaction differ between regulatory approving agencies. The cladribine US prescribing information states: -Concomitant use with myelosuppressive or other immunosuppressive drugs is not recommended. Acute short-term therapy with corticosteroids can be administered. In patients who have previously been treated with immunomodulatory or immunosuppressive drugs, consider potential additive effect, the mode of action, and duration of effect of the other drugs prior to initiation of cladribine.(1) The cladribine Canadian prescribing information states: -Use of cladribine in immunocompromised patients is contraindicated because of a risk of additive effects on the immune system. Acute short-term therapy with corticosteroids can be administered during cladribine treatment.(2) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1-2) |
CLADRIBINE, MAVENCLAD |
| Ritlecitinib/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ritlecitinib, immunosuppressives, and immunomodulators all suppress the immune system. CLINICAL EFFECTS: Concurrent use of ritlecitinib with immunosuppressives or immunomodulators may result in an increased risk of serious infections. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of ritlecitinib states that concurrent use of ritlecitinib with other JAK inhibitors, biologic immunomodulators, cyclosporine or other potent immunosuppressants is not recommended.(1) DISCUSSION: Serious infections have been reported in patients receiving ritlecitinib. Reported infections included appendicitis, COVID-19 infection (including pneumonia), and sepsis. Reports of viral reactivation, including herpes virus reactivation was reported in clinical studies with ritlecitinib.(1) |
LITFULO |
| Etrasimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Etrasimod causes reversible sequestration of lymphocytes in lymphoid tissues, resulting in a mean 55% decrease in peripheral blood lymphocyte count at 52 weeks.(1) Other immunosuppressives and immune-modulators also suppress the immune system. CLINICAL EFFECTS: Concurrent use of etrasimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious and fatal infections, such as disseminated herpetic infection, cryptococcal infection, or progressive multifocal leukoencephalopathy (PML).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications increases the risk of adverse effects. PATIENT MANAGEMENT: The etrasimod US prescribing information states etrasimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Concomitant administration of these therapies with etrasimod should be avoided because of the risk of additive immune effects during therapy and in the weeks following administration. Etrasimod's effect on peripheral lymphocytes may persist for up to 5 weeks after discontinuation.(1) When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections, cryptococcal meningitis, disseminated cryptococcal infections, and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients treated with other sphingosine-1 phosphate receptor modulators.(1) |
VELSIPITY |
| Ropeginterferon alfa-2b/Slt Immunosuppress; Immunomodulator SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ropeginterferon alfa-2b and immunosuppressives both suppress the immune system. CLINICAL EFFECTS: Concurrent use of ropeginterferon alfa-2b with immunosuppressives may result in an increased risk of serious infections. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Avoid concurrent use of myelosuppressive agents.(1-2) If concurrent use cannot be avoided, monitor for effects of excessive immunosuppression. DISCUSSION: In clinical trials, 20% of patients experienced leukopenia. Interferon alfa products may cause fatal or life-threatening infections.(1-2) |
BESREMI, BESREMI PEN |
| Deuruxolitinib/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Deuruxolitinib, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of deuruxolitinib and potent immunosuppressants may increase the risk of serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of deuruxolitinib states that concurrent use of deuruxolitinib with other JAK inhibitors, biologic immunomodulators, cyclosporine or other potent immunosuppressants is not recommended.(1) If concurrent use cannot be avoided, patients should be monitored for signs and symptoms of infection. If a patient develops a serious or opportunistic infection, interrupt deuruxolitinib treatment until the infection is controlled. DISCUSSION: Serious infections have been reported in patients receiving treatment with deuruxolitinib.(1) |
LEQSELVI |
There are 8 moderate interactions.
The clinician should assess the patient’s characteristics and take action as needed. Actions required for moderate interactions include, but are not limited to, discontinuing one or both agents, adjusting dosage, altering administration.
| Drug Interaction | Drug Names |
|---|---|
| Ruxolitinib/Fluconazole (Less Than or Equal To 200 mg) SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Fluconazole may inhibit the metabolism of ruxolitinib by CYP3A4 and CYP2C9.(1) CLINICAL EFFECTS: Concurrent use of fluconazole may increase levels of and effects from ruxolitinib, including thrombocytopenia, anemia, neutropenia, increased serious infection risk or lipid level elevations.(1) PREDISPOSING FACTORS: This interaction may be more severe in patients with a low platelet count.(1) PATIENT MANAGEMENT: For patients undergoing therapy with ruxolitinib for all indications, avoid the use of fluconazole at doses greater than 200 mg daily.(1) For patients taking fluconazole doses of less than or equal to 200 mg, reduce the dosage of ruxolitinib according to the indication. For myelofibrosis, starting doses of ruxolitinib therapy in patients concurrently taking less than or equal to 200 mg of fluconazole is based on platelet count: -In patients with a platelet count greater than or equal to 100 X 10x9/L who are receiving fluconazole at doses less than or equal to 200 mg, the recommended starting dose of ruxolitinib is 10 mg twice daily or ruxolitinib XR 22 mg once daily. -In patients with a platelet count greater than 50 X 10x9/L to less than 100 X 10x9/L who are receiving fluconazole at doses less than or equal to 200 mg, the recommended starting dose of ruxolitinib is 5 mg once daily. Do not use ruxolitinib XR.(1) For polycythemia vera, the starting dose of ruxolitinib in patients concurrently taking less than or equal to 200 mg of fluconazole is 5 mg twice daily or ruxolitinib XR 11 mg once daily.(1) In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 10 mg twice daily or more or on ruxolitinib XR doses of 22 mg once daily or more, and in whom fluconazole at doses less than or equal to 200 mg are initiated, reduce the dose of ruxolitinib by 50% (rounded up to the closest available tablet strength).(1) In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 5 mg twice daily in whom fluconazole at doses less than or equal to 200 mg is initiated, reduce the dose of ruxolitinib to 5 mg once daily. Do not use ruxolitinib XR.(1) In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 5 mg once daily or ruxolitinib XR doses of 11 mg once daily, avoid the use of fluconazole even at doses less than or equal to 200 mg, or interrupt ruxolitinib therapy for the duration of fluconazole treatment.(1) In patients with a diagnosis of acute graft-versus-host disease and concurrently taking less than or equal to 200 mg of fluconazole, the starting dose of ruxolitinib is 5 mg once daily. Do not use ruxolitinib XR.(1) In patients with a diagnosis of chronic graft-versus-host disease and concurrently taking less than or equal to 200 mg of fluconazole, the starting dose of ruxolitinib is 5 mg twice daily or ruxolitinib XR 11 mg once daily.(1) The dose should be adjusted based on monitoring of safety and efficacy.(1) DISCUSSION: Simulations in physiologically-based pharmacokinetic (PBPK) models predict that fluconazole doses of 100 mg daily will increase the area-under-curve (AUC) of ruxolitinib (10 mg twice daily) by 100%. PBPK models predict that fluconazole doses of 400 mg daily will increase the AUC of ruxolitinib (10 mg twice daily) by 300%.(1) |
FLUCONAZOLE, FLUCONAZOLE-NACL |
| Ustekinumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Ustekinumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ustekinumab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of ustekinumab recommends caution because the concurrent use of ustekinumab with immunosuppressive agents may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Ustekinumab has not been studied in combination with other immunosuppressants in psoriasis studies. In psoriatic arthritis studies, concomitant methotrexate use did not appear to influence the safety or efficacy of ustekinumab. In Crohn's disease and ulcerative colitis studies, concomitant use of immunosuppressants or corticosteroids did not appear to influence the safety or efficacy of ustekinumab. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents.(1) The most common infections reported by ustekinumab treated patients in the clinical trial periods included nasopharyngitis(8%) and upper respiratory tract infection(5%). Serious bacterial, mycobacterial, fungal, and viral infections were observed in patients receiving ustekinumab. Cases of interstitial pneumonia, eosinophilic pneumonia, and cryptogenic organizing pneumonia resulting in respiratory failure or prolonged hospitalization have been reported in patients receiving ustekinumab.(1) |
IMULDOSA, OTULFI, PYZCHIVA, PYZCHIVA AUTOINJECTOR, SELARSDI, STARJEMZA, STELARA, STEQEYMA, USTEKINUMAB, USTEKINUMAB-AAUZ, USTEKINUMAB-AEKN, USTEKINUMAB-TTWE, WEZLANA, YESINTEK |
| Ruxolitinib/Strong CYP3A4 Inhibitors SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Agents that inhibit the CYP3A4 isoenzyme may inhibit the metabolism of ruxolitinib.(1) CLINICAL EFFECTS: Concurrent use of strong CYP3A4 inhibitors may increase levels of and effects from ruxolitinib, including thrombocytopenia, risk of infection, non-melanoma skin cancer, lipid elevations.(1) PREDISPOSING FACTORS: In patients taking ruxolitinib, this interaction may be more severe in patients with a low platelet count.(1) PATIENT MANAGEMENT: Reduce the dosage of ruxolitinib when coadministered with strong CYP3A4 inhibitors. Dose modifications of ruxolitinib in patients on concomitant strong CYP3A4 inhibitors depend on the indication. For myelofibrosis, starting doses of ruxolitinib therapy in patients concurrently taking strong CYP3A4 inhibitors is based on platelet count: -In patients with a platelet count greater than or equal to 100 X 10x9/L who are receiving a strong inhibitor of CYP3A4, the recommended starting dose of ruxolitinib is 10 mg twice daily or ruxolitinib XR 22 mg once daily. -In patients with a platelet count greater than 50 X 10x9/L to less than 100 X 10x9/L who are receiving a strong inhibitor of CYP3A4, the recommended starting dose of ruxolitinib is 5 mg once daily. Do not use ruxolitinib XR. For polycythemia vera, the starting dose of ruxolitinib in patients concurrently taking a strong CYP3A4 inhibitor is 5 mg twice daily or ruxolitinib XR 11 mg once daily. In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 10 mg twice daily or more or on ruxolitinib XR doses of 22 mg once daily or more, and in whom a strong CYP3A4 inhibitor is initiated, reduce the dose of ruxolitinib by 50% (rounded up to the closest available tablet strength). In patients with a diagnosis of myelofibrosis or polycythemia vera who are stabilized on ruxolitinib doses of 5 mg twice daily in whom a strong CYP3A4 inhibitor is initiated, reduce the dose of ruxolitinib to 5 mg once daily. Do not use ruxolitinib XR. In patients with a diagnosis of myelofibrosis or polycythemia vera stabilized on ruxolitinib doses of 5 mg once daily or ruxolitinib XR doses of 11 mg once daily, avoid the use of strong CYP3A4 inhibitors or interrupt ruxolitinib therapy for the duration of the CYP3A4 inhibitor treatment. In patients with a diagnosis of acute or chronic graft-versus-host disease, no dose adjustment is recommended for concurrent use of strong CYP3A4 inhibitors in patients on ruxolitinib. It is recommended to increase the frequency of blood count monitoring when ruxolitinib is used with strong CYP3A4 inhibitors for acute or chronic graft-versus-host disease. The dose should be adjusted based on monitoring of safety and efficacy.(1) DISCUSSION: In healthy subjects, ketoconazole (200 mg twice daily for 4 days) increased the concentration maximum (Cmax), area-under-curve (AUC), and half-life of a single dose of ruxolitinib (10 mg) by 33%, 91%, and 62%, respectively. There was also a corresponding increase in pSTAT3 inhibition, a pharmacodynamic marker for ruxolitinib.(1) In healthy subjects, erythromycin (a moderate inhibitor of CYP3A4, 500 mg twice daily for 4 days) increased the Cmax and AUC of a single dose of ruxolitinib (10 mg) by 8% and 27%, respectively. Therefore, no dosage adjustment is recommended with moderate or mild inhibitors of CYP3A4.(1) Strong inhibitors of CYP3A4 include: adagrasib, boceprevir, ceritinib, clarithromycin, cobicistat, ensitrelvir, idelalisib, indinavir, itraconazole, josamycin, ketoconazole, lonafarnib, lopinavir, mibefradil, mifepristone, nefazodone, nelfinavir, nirmatrelvir/ritonavir, paritaprevir, posaconazole, relacorilant, ribociclib, saquinavir, telaprevir, telithromycin, tipranavir, troleandomycin, tucatinib, or voriconazole.(2,3) |
APTIVUS, CLARITHROMYCIN, CLARITHROMYCIN ER, EVOTAZ, GENVOYA, ITRACONAZOLE, ITRACONAZOLE MICRONIZED, KALETRA, KETOCONAZOLE, KISQALI, KORLYM, KRAZATI, LANSOPRAZOL-AMOXICIL-CLARITHRO, LIFYORLI, LOPINAVIR-RITONAVIR, MIFEPREX, MIFEPRISTONE, NEFAZODONE HCL, NOXAFIL, OMECLAMOX-PAK, PAXLOVID, POSACONAZOLE, PREZCOBIX, RECORLEV, SPORANOX, STRIBILD, SYMTUZA, TOLSURA, TUKYSA, VFEND, VFEND IV, VIRACEPT, VOQUEZNA TRIPLE PAK, VORICONAZOLE, VORICONAZOLE (HPBCD), XOCOVA, ZOKINVY, ZYDELIG, ZYKADIA |
| COVID-19 Vaccines/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Immunosuppressants and immunomodulators may prevent the immune system from properly responding to the COVID-19 vaccine.(1-3) CLINICAL EFFECTS: Administration of a COVID-19 vaccine with immunosuppressants or immunomodulators may interfere with vaccine-induced immune response and impair the efficacy of the vaccine. However, patients should be offered and given a COVID-19 vaccine even if the use and timing of immunosuppressive agents cannot be adjusted.(1-3) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The Centers for Disease Control and Prevention (CDC),(1) Infectious Diseases Society of America (IDSA),(2) and the American College of Rheumatology (ACR)(3) have published guidances for COVID-19 vaccination in patients on immunosuppressants. The CDC states that all immunocompromised patients over 6 months of age should receive at least 1 dose of COVID-19 vaccine if eligible. See the CDC's Interim Clinical Considerations for Use of COVID-19 Vaccines for specific recommendations based on age, vaccination history, and vaccine manufacturer.(1) The CDC advises planning for vaccination at least 2 weeks before starting or resuming immunosuppressive therapy.(1) IDSA recommends timing COVID-19 vaccination at least 2 weeks before starting or at least 3 months after completing immunosuppressive therapy.(2) The ACR states that in general, immunosuppressants and immunomodulators should be held for 1-2 weeks after each vaccine dose.(3) Patients should be offered and given a COVID-19 vaccine even if the use and timing of immunosuppressive agents cannot be adjusted, though the immune response will likely be blunted. COVID-19 vaccines should not be delayed in patients taking immunosuppressive therapies.(1-2) See below for specific recommendations for certain agents. B-cell depleting agents, including rituximab: The CDC states that the utility of B-cell quantification to guide clinical care is not known and is not recommended. Patients who receive B-cell depleting therapy on a continuing basis should receive COVID-19 vaccines about 4 weeks before the next scheduled dose. For patients who received 1 or more doses of COVID-19 vaccine during treatment with B-cell-depleting therapies that were administered over a limited period (e.g., as part of a treatment regimen for certain malignancies), revaccination may be considered according to the current CDC recommendations for unvaccinated patients. The suggested interval to start revaccination is about 6 months after completion of the B-cell-depleting therapy.(1) IDSA recommends waiting for at least 3-6 months after the last infusion of B-cell depleting therapy before administering COVID-19 vaccines.(2) The ACR recommends consulting with the rheumatologist to determine optimal timing of COVID-19 vaccination. Measuring CD19 B cells may be considered to determine need for a booster vaccine dose. If B cell levels are not measured, a supplemental vaccine dose 2-4 weeks before the next scheduled dose of rituximab is recommended.(3) Recipients of hematopoietic cell transplant or CAR-T-cell therapy who received one or more doses of COVID-19 vaccine prior to or during treatment should undergo revaccination following the current CDC recommendations for unvaccinated patients. Revaccination should start at least 3 months (12 weeks) after transplant or CAR-T-cell therapy.(1,2) The CDC includes abatacept, cyclophosphamide, and TNF-alpha and cytokine inhibitors in their general recommendation to hold therapy for at least 2 weeks following vaccination (1) while the ACR provides different recommendations:(3) *Abatacept: - Subcutaneous abatacept should be withheld for 1-2 weeks after each vaccine dose, as disease activity allows. - For intravenous abatacept, time administration so that vaccination will occur 1 week before the next abatacept infusion. *Cyclophosphamide: When feasible, administer cyclophosphamide 1 week after each COVID-19 vaccine dose. *TNF-alpha inhibitors and cytokine inhibitors: The ACR was not able to reach consensus on whether to modify dosing or timing of these agents with COVID-19 vaccination. DISCUSSION: IDSA recommendations are based on cohort and case control studies in immunocompromised patients that found low to modest vaccine effectiveness (37-61%) but lower risks of COVID-19 association hospitalization, COVID-19 related mortality, and critical illness.(2) The ACR convened a COVID-19 Vaccine Guidance Task Force to provide guidance on optimal use of COVID-19 vaccines in rheumatology patients. These recommendations are based on limited clinical evidence of COVID-19 vaccines in patients without rheumatic and musculoskeletal disorders and evidence of other vaccines in this patient population.(3) The ACR recommendation for rituximab is based on studies of humoral immunity following receipt of other vaccines. These studies have uncertain generalizability to vaccination against COVID-19, as it is unknown if efficacy is attributable to induction of host T cells versus B cell (antibody-based) immunity.(3) The ACR recommendation for mycophenolate is based on preexisting data of mycophenolate on non-COVID-19 vaccine immunogenicity. Emerging data suggests that mycophenolate may impair SARS-CoV-2 vaccine response in rheumatic and musculoskeletal disease and transplant patients.(3) The ACR recommendation for methotrexate is based on data from influenza vaccines and pneumococcal vaccines with methotrexate.(3) The ACR recommendation for JAK inhibitors is based on concerns related to the effects of JAK inhibitors on interferon signaling that may result in a diminished vaccine response.(3) The ACR recommendation for subcutaneous abatacept is based on several studies suggesting a negative effect of abatacept on vaccine immunogenicity. The first vaccine dose primes naive T cells, naive T cell priming is inhibited by CTLA-4, and abatacept is a CTLA-4Ig construct. CTLA-4 should not inhibit boosts of already primed T cells at the time of the second vaccine dose.(3) |
COMIRNATY 2026-2027 (12Y UP), COMIRNATY 2026-2027(5-11Y), MNEXSPIKE 2026-2027 (12Y UP), NUVAXOVID 2026-2027, SPIKEVAX 2026-2027 (12Y UP), SPIKEVAX 2026-2027 (6M-11Y) |
| Sarilumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Sarilumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of sarilumab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of sarilumab recommends caution because the concurrent use of sarilumab with immunosuppressive agents may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Sarilumab was studied as monotherapy and in combination with methotrexate or conventional disease modifying antirheumatic drugs (DMARDs) in rheumatoid arthritis studies. Sarilumab has not been studied with biological DMARDs and concurrent use should be avoided. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents.(1) The most common infections reported by sarilumab treated patients in the clinical trial periods included pneumonia and cellulitis. Serious bacterial, mycobacterial, fungal, and viral infections were observed in patients receiving sarilumab. Cases of tuberculosis, candidiasis, and pneumocystis with sarilumab have been reported.(1) |
KEVZARA |
| Ublituximab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Ublituximab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ublituximab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The US manufacturer of ublituximab recommends caution because the concurrent use of ublituximab with immunomodulating or immunosuppressive agents, including immunosuppressant doses of corticosteroids, may increase the risk of infection.(1) If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents. When switching from agents with immune effects, the half-life and mechanism of action of these drugs must be taken into consideration in order to prevent additive immunosuppressive effects.(1) DISCUSSION: The most common infections reported by ublituximab-treated patients in the clinical trial periods included upper respiratory tract infections and urinary tract infections. Serious, including life-threatening or fatal, bacterial and viral infections were observed in patients receiving ublituximab.(1) Serious and/or fatal bacterial, fungal, and new or reactivated viral infections have been associated with other anti-CD20 B-cell depleting therapies. There were no cases of progressive multifocal leukoencephalopathy (PML) reported during the clinical trials; however, there have been reports of PML during or following completion of other anti-CD20 B-cell depleting therapies.(1) |
BRIUMVI |
| Tocilizumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Tocilizumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of tocilizumab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of tocilizumab recommends caution because the concurrent use of tocilizumab with immunosuppressive agents may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Tocilizumab was studied as monotherapy and in combination with methotrexate, non-biologic DMARDs or corticosteroids, depending on the indication. Tocilizumab has not been studied with biological DMARDs and concurrent use should be avoided. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents.(1) The most common infections reported by tocilizumab treated patients in the clinical trial periods included pneumonia, urinary tract infection, cellulitis, herpes zoster, gastroenteritis, diverticulitis, sepsis and bacterial arthritis. Serious bacterial, mycobacterial, fungal, and viral infections were observed in patients receiving tocilizumab. Cases of tuberculosis, cryptococcus, aspergillosis, candidiasis, and pneumocystosis have been reported.(1) |
ACTEMRA, ACTEMRA ACTPEN, AVTOZMA, AVTOZMA AUTOINJECTOR, TOFIDENCE, TYENNE, TYENNE AUTOINJECTOR |
| Cladribine Oncology Inj/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Cladribine in combination with immunosuppressives and immune-modulators all suppress the immune system.(1-4) CLINICAL EFFECTS: Concurrent use of cladribine with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections.(1-4) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: Recommendations for cladribine regarding this interaction differ between regulatory approving agencies. The cladribine US, UK, and Australian prescribing information state: -Caution should be exercised if cladribine injection is administered before, after, or in conjunction with other drugs known to cause immunosuppression or myelosuppression.(1-3) The cladribine Canadian prescribing information states: -Proceed carefully in patients with severe bone marrow impairment of any etiology since further suppression of bone marrow function should be anticipated.(4) DISCUSSION: Severe bone marrow suppression, including neutropenia, anemia and thrombocytopenia, has been commonly observed in patients treated with cladribine injection, especially at high doses.(1-4) |
CLADRIBINE |
The following contraindication information is available for JAKAFI (ruxolitinib phosphate):
Drug contraindication overview.
*The manufacturer states that there are no known contraindications to the use of ruxolitinib phosphate.
*The manufacturer states that there are no known contraindications to the use of ruxolitinib phosphate.
There are 2 contraindications.
Absolute contraindication.
| Contraindication List |
|---|
| Lactation |
| Progressive multifocal leukoencephalopathy |
There are 19 severe contraindications.
Adequate patient monitoring is recommended for safer drug use.
| Severe List |
|---|
| Active tuberculosis |
| Anemia |
| Atherosclerotic cardiovascular disease |
| Child-pugh class A hepatic impairment |
| Child-pugh class B hepatic impairment |
| Child-pugh class C hepatic impairment |
| Chronic kidney disease stage 3A (moderate) GFR 45-59 ml/min |
| Chronic kidney disease stage 3B (moderate) GFR 30-44 ml/min |
| Chronic kidney disease stage 4 (severe) GFR 15-29 ml/min |
| Chronic kidney disease stage 5 (failure) GFr<15 ml/min |
| Disease of liver |
| Infection |
| Malignancy |
| Malignant lymphoma |
| Neutropenic disorder |
| Thrombocytopenic disorder |
| Thromboembolic disorder |
| Thrombotic disorder |
| Viral hepatitis B |
There are 4 moderate contraindications.
Clinically significant contraindication, where the condition can be managed or treated before the drug may be given safely.
| Moderate List |
|---|
| Basal cell carcinoma of skin |
| Kidney disease with likely reduction in glomerular filtration rate (GFr) |
| Merkel cell carcinoma |
| Squamous cell carcinoma |
The following adverse reaction information is available for JAKAFI (ruxolitinib phosphate):
Adverse reaction overview.
In patients with myelofibrosis and polycythemia vera treated with ruxolitinib, the most common adverse hematologic reactions (reported in >20%) include thrombocytopenia and anemia. The most common nonhematologic adverse reactions (reported in >=15%) include bruising, dizziness, headache, and diarrhea. In patients with acute GVHD treated with ruxolitinib, the most common adverse hematologic reactions (reported in >50%) include anemia, thrombocytopenia, and neutropenia.
The most common nonhematologic adverse reactions (reported in >50%) include infections and edema. In patients with chronic GVHD treated with ruxolitinib, the most common adverse hematologic reactions (reported in >35%) include anemia and thrombocytopenia. The most common nonhematologic adverse reactions (reported in >=20%) include infections and viral infections.
In patients with myelofibrosis and polycythemia vera treated with ruxolitinib, the most common adverse hematologic reactions (reported in >20%) include thrombocytopenia and anemia. The most common nonhematologic adverse reactions (reported in >=15%) include bruising, dizziness, headache, and diarrhea. In patients with acute GVHD treated with ruxolitinib, the most common adverse hematologic reactions (reported in >50%) include anemia, thrombocytopenia, and neutropenia.
The most common nonhematologic adverse reactions (reported in >50%) include infections and edema. In patients with chronic GVHD treated with ruxolitinib, the most common adverse hematologic reactions (reported in >35%) include anemia and thrombocytopenia. The most common nonhematologic adverse reactions (reported in >=20%) include infections and viral infections.
There are 17 severe adverse reactions.
| More Frequent | Less Frequent |
|---|---|
|
Abnormal hepatic function tests Anemia Neutropenic disorder Thrombocytopenic disorder |
Herpes zoster Hypertension Increased alanine transaminase Increased aspartate transaminase Infection Thrombotic disorder Viral infection |
| Rare/Very Rare |
|---|
|
Active tuberculosis Bacterial infection Herpes simplex infection Hypoglycemic disorder Opportunistic fungal infection Progressive multifocal leukoencephalopathy |
There are 22 less severe adverse reactions.
| More Frequent | Less Frequent |
|---|---|
|
Acute abdominal pain Bruising Diarrhea Dizziness Dyspnea Fatigue Headache disorder Hypercholesterolemia Muscle spasm |
Constipation Cough Edema Epistaxis Flatulence Pharyngitis Skin rash Urinary tract infection Weight gain |
| Rare/Very Rare |
|---|
|
Basal cell carcinoma of skin Hypertriglyceridemia Merkel cell carcinoma Squamous cell carcinoma |
The following precautions are available for JAKAFI (ruxolitinib phosphate):
Safety and efficacy of ruxolitinib have not been established in pediatric patients younger than 12 years of age with acute or chronic GVHD or in pediatric patients for the treatment of myelofibrosis and polycythemia vera.
Contraindicated
Severe Precaution
Management or Monitoring Precaution
Contraindicated
| None |
Severe Precaution
| None |
Management or Monitoring Precaution
| None |
Adverse developmental outcomes, including decreased fetal weight, have been observed in animal studies when ruxolitinib was administered to pregnant rabbits and rats at dosages associated with maternal toxicity. There are no studies of ruxolitinib in pregnant women to inform a drug-associated risk.
Ruxolitinib and/or its metabolites are distributed into milk in rats; it is not known whether ruxolitinib is distributed into human milk. Because of the potential for adverse reactions (i.e., thrombocytopenia, anemia) to ruxolitinib in the breastfed infant, and because many drugs are present in human milk, discontinue breast-feeding during ruxolitinib therapy and for 2 weeks after the final dose of the drug.
In clinical studies of ruxolitinib, approximately 52% of patients with myelofibrosis were 65 years of age or older and 15% of patients were 75 years of age or older. In clinical studies of ruxolitinib in patients with chronic GVHD, approximately 11% were 65 years of age or older. No overall differences in safety or efficacy relative to younger adults were observed in clinical trials. Clinical studies of patients with acute GVHD did not include sufficient numbers of subjects 65 years of age and older to determine whether they respond differently than younger adults.
The following prioritized warning is available for JAKAFI (ruxolitinib phosphate):
No warning message for this drug.
No warning message for this drug.
The following icd codes are available for JAKAFI (ruxolitinib phosphate)'s list of indications:
| Chronic graft-versus-host disease | |
| D89.811 | Chronic graft-versus-host disease |
| Graft-versus-host disease | |
| D89.81 | Graft-versus-host disease |
| D89.810 | Acute graft-versus-host disease |
| D89.811 | Chronic graft-versus-host disease |
| D89.812 | Acute on chronic graft-versus-host disease |
| D89.813 | Graft-versus-host disease, unspecified |
| Myelofibrosis | |
| D47.4 | Osteomyelofibrosis |
| D75.81 | Myelofibrosis |
| Polycythemia vera | |
| D45 | Polycythemia vera |
Formulary Reference Tool