Please wait while the formulary information is being retrieved.
Drug overview for BLEOMYCIN SULFATE (bleomycin sulfate):
Generic name: BLEOMYCIN SULFATE (BLEE-oh-MYE-sin)
Drug class: Bleomycin
Therapeutic class: Antineoplastics
Bleomycin sulfate, a mixture of basic cytotoxic glycopeptide antibiotics produced by Streptomyces verticillus (bleomycin A2 and bleomycin B2 are the major components), is an antineoplastic agent.
No enhanced Uses information available for this drug.
DRUG IMAGES
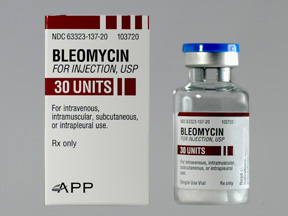 BLEOMYCIN SULFATE 30 UNIT VIAL
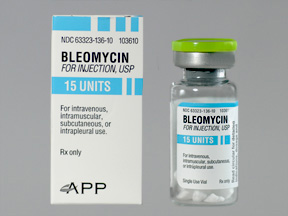 BLEOMYCIN SULFATE 15 UNIT VIAL
The following indications for BLEOMYCIN SULFATE (bleomycin sulfate) have been approved by the FDA:
Indications:
Diffuse large B-cell lymphoma
Follicular lymphoma
Hodgkin's lymphoma
Non-Hodgkin's lymphoma
Penile carcinoma
Pleural malignant effusion
Squamous cell carcinoma of head and neck
Squamous cell carcinoma of vulva
Testicular germ cell tumor
Professional Synonyms:
Anemia lymphatica
Epidermoid carcinoma of the head and neck
Follicular B-cell lymphoma
Follicular B-cell non-Hodgkin's lymphoma
Germ cell tumor of testis
Hodgkin's disease
Malignancy of penis
Malignant neoplasm of penis
Malignant pleural effusion
Malignant tumor of penis
Non-Hodgkin's type lymphoma
Penile cancer
SCC of vulva
The following dosing information is available for BLEOMYCIN SULFATE (bleomycin sulfate):
Dosage of bleomycin sulfate is expressed in terms of bleomycin. Dosage of bleomycin must be based on the tolerance and clinical response of the patient in order to obtain optimum therapeutic results with minimum adverse effects. Clinicians should consult published protocols for the dosage of bleomycin and other chemotherapeutic agents and the method and sequence of administration.
Because of the increased incidence of toxicity, especially pulmonary toxicity, associated with large cumulative dosages, cumulative dosages exceeding 400 units of bleomycin in adults should be given with great caution. When bleomycin is used in conjunction with other antineoplastic agents, pulmonary toxicity may occur at lower cumulative dosages of bleomycin.
Clearance of bleomycin may be reduced in patients with renal impairment; there are no guidelines for dosage adjustments in such patients, but the manufacturer states that the drug should be used with extreme caution in patients with severe renal impairment.
No enhanced Administration information available for this drug.
No dosing information available.
No generic dosing information available.
The following drug interaction information is available for BLEOMYCIN SULFATE (bleomycin sulfate):
There are 5 contraindications.
These drug combinations generally should not be dispensed or administered to the same patient. A manufacturer label warning that indicates the contraindication warrants inclusion of a drug combination in this category, regardless of clinical evidence or lack of clinical evidence to support the contraindication.
| Drug Interaction | Drug Names |
|---|---|
| Efalizumab; Natalizumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: Natalizumab,(1-3) efalizumab,(4) immunosuppressives, and immunomodulators all suppress the immune system. CLINICAL EFFECTS: Concurrent use of natalizumab(1-3) or efalizumab(4) with immunosuppressives or immunomodulators may result in an increased risk of infections, including progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV). PREDISPOSING FACTORS: Previous JCV infection, longer duration of natalizumab treatment - especially if greater than 2 years, and prior or concomitant treatment with immunosuppressant medication are all independent risk factors which increase the risk for PML.(1,5) The FDA has estimated PML incidence stratified by risk factors: If anti-JCV antibody positive, no prior immunosuppressant use and natalizumab treatment less than 25 months, incidence <1/1,000. If anti-JCV antibody positive, history of prior immunosuppressant use and natalizumab treatment less than 25 months, incidence 2/1,000 If anti-JCV antibody positive, no prior immunosuppressant use and natalizumab treatment 25-48 months, incidence 4/1,000 If anti-JCV antibody positive, history of prior immunosuppressant use and natalizumab treatment 25-48 months, incidence 11/1,000. PATIENT MANAGEMENT: The US manufacturer of natalizumab states patients with Crohn's disease should not receive concurrent immunosuppressants, with the exception of limited overlap of corticosteroids, due to the increased risk for PML. For new natalizumab patients currently receiving chronic oral corticosteroids for Crohn's Disease, begin corticosteroid taper when therapeutic response to natalizumab has occurred. If corticosteroids cannot be discontinued within six months of starting natalizumab, discontinue natalizumab.(3) The US manufacturer of natalizumab states that natalizumab should not ordinarily be used in multiple sclerosis patients receiving immunosuppressants or immunomodulators due to the increased risk for PML. Immunosuppressives include, but are not limited to azathioprine, cyclophosphamide, cyclosporine, mercaptopurine, methotrexate, mitoxantrone, mycophenolate, and corticosteroids.(3,6) The UK manufacturer of natalizumab states that concurrent use with immunosuppressives or antineoplastic agents is contraindicated.(1) The Canadian manufacturer of natalizumab states that natalizumab should not be used with immunosuppressive or immunomodulatory agents.(2) The US manufacturer of certolizumab states that concurrent therapy with natalizumab is not recommended.(7) DISCUSSION: Progressive multifocal leukoencephalopathy has been reported in patients receiving concurrent natalizumab were recently or concomitantly taking immunomodulators or immunosuppressants.(1-5,8,9) In a retrospective cohort study of multiple sclerosis patients newly initiated on a disease-modifying therapy, use of high-efficacy agents (alemtuzumab, natalizumab, or ocrelizumab) resulted in the same risk of overall infections as moderate-efficacy agents, but there was an elevated risk of serious infections (adjusted hazard ratio [aHR] = 1.24, 95% confidence interval (CI) = 1.06-1.44) and UTIs (aHR = 1.21, 95% CI = 1.14-1.30).(10) |
TYRUKO, TYSABRI |
| Live Vaccines; Live BCG/Selected Immunosuppressive Agents SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: A variety of disease modifying agents suppress the immune system. Immunocompromised patients may be at increased risk for uninhibited replication after administration of live, attenuated vaccines or intravesicular BCG. Immune response to vaccines may be decreased during periods of immunocompromise.(1) CLINICAL EFFECTS: The expected serum antibody response may not be obtained and/or the vaccine may result in illness.(1) After instillation of intravesicular BCG, immunosuppression may interfere with local immune response, or increase the severity of mycobacterial infection following inadvertent systemic exposure.(2) PREDISPOSING FACTORS: Immunosuppressive diseases (e.g. hematologic malignancies, HIV disease), treatments (e.g. radiation) and drugs may all increase the magnitude of immunodeficiency. PATIENT MANAGEMENT: The Centers for Disease Control(CDC) Advisory Committee on Immunization Practices (ACIP) states that live-virus and live, attenuated vaccines should not be administered to patients who are immunocompromised. The magnitude of immunocompromise and associated risks should be determined by a physician.(1) For patients scheduled to receive chemotherapy, vaccination should ideally precede the initiation of chemotherapy by 14 days. Patients vaccinated while on immunosuppressive therapy or in the 2 weeks prior to starting therapy should be considered unimmunized and should be revaccinated at least 3 months after discontinuation of therapy.(1) Patients who receive anti-B cell therapies should not receive live vaccines for at least 6 months after such therapies due to a prolonged duration of immunosuppression. An exception is the Zoster vaccine, which can be given at least 1 month after receipt of anti-B cell therapies.(1) The US manufacturer of abatacept states live vaccines should not be given during or for up to 3 months after discontinuation of abatacept.(2) The US manufacturer of live BCG for intravesicular treatment of bladder cancer states use is contraindicated in immunosuppressed patients.(3) The US manufacturer of daclizumab states live vaccines are not recommended during and for up to 4 months after discontinuation of treatment.(4) The US manufacturer of guselkumab states that live vaccines should be avoided during treatment with guselkumab.(5) The US manufacturer of inebilizumab-cdon states that live vaccines are not recommended during treatment and after discontinuation until B-cell repletion. Administer all live vaccinations at least 4 weeks prior to initiation of inebilizumab-cdon.(6) The US manufacturer of ocrelizumab states that live vaccines are not recommended during treatment and until B-cell repletion occurs after discontinuation of therapy. Administer all live vaccines at least 4 weeks prior to initiation of ocrelizumab.(7) The US manufacturer of ozanimod states that live vaccines should be avoided during and for up to 3 months after discontinuation of ozanimod.(8) The US manufacturer of siponimod states that live vaccines are not recommended during treatment and for up to 4 weeks after discontinuation of treatment.(9) The US manufacturer of ustekinumab states BCG vaccines should not be given in the year prior to, during, or the year after ustekinumab therapy.(10) The US manufacturer of satralizumab-mwge states that live vaccines are not recommended during treatment and should be administered at least four weeks prior to initiation of satralizumab-mwge.(11) The US manufacturer of ublituximab-xiiy states that live vaccines are not recommended during treatment and until B-cell recovery. Live vaccines should be administered at least 4 weeks prior to initiation of ublituximab-xiiy.(12) The US manufacturer of etrasimod states that live vaccines should be avoided during and for 5 weeks after treatment. Live vaccines should be administered at least 4 weeks prior to initiation of etrasimod.(13) The US manufacturer of emapalumab-lzsg states that live vaccines should not be administered to patients receiving emapalumab-lzsg and for at least 4 weeks after the last dose of emapalumab-lzsg. The safety of immunization with live vaccines during or following emapalumab-lzsg therapy has not been studied.(14) The US manufacturer of sibeprenlimab-szsi states live vaccines should not be given within 30 days prior to initiation or during treatment with sibeprenlimab-szsi.(15) DISCUSSION: Killed or inactivated vaccines do not pose a danger to immunocompromised patients.(1) Patients with a history of leukemia who are in remission and have not received chemotherapy for at least 3 months are not considered to be immunocompromised.(1) |
ACAM2000 (NATIONAL STOCKPILE), ADENOVIRUS TYPE 4, ADENOVIRUS TYPE 4 AND TYPE 7, ADENOVIRUS TYPE 7, BCG (TICE STRAIN), BCG VACCINE (TICE STRAIN), DENGVAXIA, ERVEBO (NATIONAL STOCKPILE), FLUMIST 2026-2027, FLUMIST HOME 2026-2027, M-M-R II VACCINE, PRIORIX, PROQUAD, ROTARIX, ROTATEQ, STAMARIL, VARIVAX VACCINE, VAXCHORA ACTIVE COMPONENT, VAXCHORA VACCINE, VIVOTIF, YF-VAX |
| Bleomycin/Brentuximab SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: The exact mechanism is unknown. CLINICAL EFFECTS: Concurrent use of brentuximab with bleomycin-based chemotherapy regimens may result in non-infectious pulmonary toxicity.(1,2) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Concurrent use of brentuximab with bleomycin-based chemotherapy regimens is contraindicated.(1,2) In patients who have received concurrent therapy, monitor for signs of pulmonary toxicity, including cough and dyspnea. Patients with symptoms of pulmonary toxicity may respond to corticosteroid therapy.(1,2) DISCUSSION: In a clinical trial that compared the use of brentuximab with Adriamycin (doxorubicin), bleomycin, vinblastine, and dacarbazine (ABVD) to the use of brentuximab with Adriamycin (doxorubicin), vinblastine, and dacarbazine (AVD), 40% of patients receiving brentuximab with ABVD experienced pulmonary toxicity. No patients receiving brentuximab with AVD have experienced pulmonary toxicity to date. Historical controls suggest a frequency of pulmonary toxicity of 10-25% in bleomycin-based regimens.(1) |
ADCETRIS |
| Talimogene laherparepvec/Selected Immunosuppressants SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: Talimogene laherparepvec is a live, attenuated herpes simplex virus.(1) CLINICAL EFFECTS: Concurrent use of talimogene laherparepvec in patients receiving immunosuppressive therapy may cause a life-threatening disseminated herpetic infection.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Talimogene laherparepvec is contraindicated in immunosuppressed patients.(1) The magnitude of immunocompromise and associated risks due to immunosuppressant drugs should be determined by a physician. DISCUSSION: Concurrent use of talimogene laherparepvec in patients receiving immunosuppressive therapy may cause a life-threatening disseminated herpetic infection.(1) |
IMLYGIC |
| Nadofaragene Firadenovec/Selected Immunosuppressants SEVERITY LEVEL: 1-Contraindicated Drug Combination: This drug combination is contraindicated and generally should not be dispensed or administered to the same patient. MECHANISM OF ACTION: Nadofaragene firadenovec may contain low levels of replication-competent adenovirus.(1) CLINICAL EFFECTS: Concurrent use of nadofaragene firadenovec in patients receiving immunosuppressive therapy may cause disseminated adenovirus infection.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Individuals who are immunosuppressed or immune-deficient should not receive nadofaragene firadenovec.(1) DISCUSSION: Nadofaragene firadenovec is a non-replicating adenoviral vector-based gene therapy but may contain low levels of replication-competent adenovirus. Immunocompromised persons, including those receiving immunosuppressant therapy, may be at risk for disseminated adenovirus infection.(1) |
ADSTILADRIN |
There are 16 severe interactions.
These drug interactions can produce serious consequences in most patients. Actions required for severe interactions include, but are not limited to, discontinuing one or both agents, adjusting dosage, altering administration scheduling, and providing additional patient monitoring. Review the full interaction monograph for more information.
| Drug Interaction | Drug Names |
|---|---|
| Tofacitinib/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Concurrent use of tofacitinib and azathioprine, other biologic disease-modifying antirheumatic drugs (DMARDs), or potent immunosuppressants may result in additive or synergistic effects on the immune system.(1) CLINICAL EFFECTS: Concurrent use of tofacitinib and azathioprine, other biologic DMARDs, or potent immunosuppressants use may increase the risk of serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Tofacitinib should not be used concurrently with azathioprine, other biologic DMARDs, or cyclosporine.(1) Patient should be monitored for decreases in lymphocytes and neutrophils. Therapy should be adjusted based on the indication. - For all indications: If absolute neutrophil count (ANC) or lymphocyte count is less than 500 cells/mm3, discontinue tofacitinib. - For rheumatoid arthritis or psoriatic arthritis and absolute neutrophil count (ANC) 500 to 1000 cells/mm3: interrupt dosing. When ANC is greater than 1000 cells/mm3, resume Xeljanz 5 mg twice daily or Xeljanz XR 11 mg once daily. - For ulcerative colitis and ANC 500 to 1000 cells/mm3: -If taking Xeljanz 10 mg twice daily, decrease to 5 mg twice daily. When ANC is greater than 1000 cells/mm3, increase to 10 mg twice daily based on clinical response. -If taking Xeljanz 5 mg twice daily, interrupt dosing. When ANC is greater than 1000 cells/mm3, resume 5 mg twice daily. -If taking Xeljanz XR 22 mg once daily, decrease to 11 mg once daily. When ANC is greater than 1000 cells/mm3, increase to 22 mg once daily based on clinical response. -If taking Xeljanz XR 11 mg once daily, interrupt dosing. When ANC is greater than 1000 cells/mm3, resume 11 mg once daily. - For polyarticular course juvenile idiopathic arthritis (pcJIA) and ANC 500 to 1000 cells/mm3: interrupt dosing until ANC is greater than 1000 cells/mm3.(1) DISCUSSION: Concurrent use of tofacitinib and azathioprine, other biologic DMARDs, or potent immunosuppressants may increase the risk of infection.(1) Serious infections due to bacterial, mycobacterial, invasive fungal, viral, or other opportunistic pathogens have been reported in patients receiving tofacitinib. Some patients presented with disseminated disease and were often taking concomitant immunomodulating agents. In the ulcerative colitis population, a greater risk of serious infections was seen with a higher tofacitinib dose. In 7 placebo-controlled rheumatoid arthritis trials (0-3 months exposure), the overall frequency of infections was 20% in the tofacitinib 5 mg twice daily group and 22% in the tofacitinib 10 mg twice daily group compared to 18% in the placebo group. Serious infections were reported in 11 patients (1.7 events per 100 patient-years) with a rate difference between treatment groups of 1.1 (-0.4, 2.5) events per 100 patient-years for both tofacitinib 5 mg twice daily and 10 mg twice daily. During 0-12 months exposure, serious infections were reported in 34 patients (2.7 events per 100 patient years) in the tofacitinib 5 mg twice daily group and 33 patients (2.7 events per 100 patient years) in the tofacitinib 10 mg twice daily group.(1) |
TOFACITINIB CITRATE, TOFACITINIB CITRATE ER, XELJANZ, XELJANZ XR |
| Selected Multiple Sclerosis Agents/Immunosuppressants; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ocrelizumab or ofatumumab in combination with immunosuppressives and immune-modulators all suppress the immune system.(1,2) CLINICAL EFFECTS: Concurrent use of ocrelizumab or ofatumumab with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1,2) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The ocrelizumab US prescribing information states: - Ocrelizumab and other immune-modulating or immunosuppressive therapies, (including immunosuppressant doses of corticosteroids) are expected to increase the risk of immunosuppression, and the risk of additive immune system effects must be considered if these therapies are coadministered with ocrelizumab. When switching from drugs with prolonged immune effects, such as daclizumab, fingolimod, natalizumab, teriflunomide, or mitoxantrone, the duration and mode of action of these drugs must be considered to avoid unintended additive immunosuppressive effects when initiating ocrelizumab.(1) The ofatumumab US prescribing information states: - Ofatumumab and other immunosuppressive therapies (including systemic corticosteroids) may have the potential for increased immunosuppressive effects and increase the risk of infection. When switching between therapies, the duration and mechanism of action of each therapy should be considered due to the potential for additive immunosuppressive effects. Ofatumumab for MS therapy has not been studied in combination with other MS agents that suppress the immune system.(2) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1,2) In a retrospective cohort study of multiple sclerosis patients newly initiated on a disease-modifying therapy, use of high-efficacy agents (alemtuzumab, natalizumab, or ocrelizumab) resulted in the same risk of overall infections as moderate-efficacy agents, but there was an elevated risk of serious infections (adjusted hazard ratio [aHR] = 1.24, 95% confidence interval (CI) = 1.06-1.44) and UTIs (aHR = 1.21, 95% CI = 1.14-1.30).(3) |
KESIMPTA PEN, OCREVUS, OCREVUS ZUNOVO |
| Upadacitinib/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Upadacitinib, immunosuppressives, and immunomodulators all suppress the immune system. CLINICAL EFFECTS: Concurrent use of upadacitinib with immunosuppressives or immunomodulators may result in an increased risk of serious infections. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of upadacitinib states that concurrent use of upadacitinib with immunosuppressives or immunomodulators is not recommended. DISCUSSION: Serious infections have been reported in patients receiving upadacitinib. Reported infections included pneumonia, cellulitis, tuberculosis, multidermatomal herpes zoster, oral/esophageal candidiasis, cryptococcosis. Reports of viral reactivation, including herpes virus reactivation and hepatitis B reactivation, were reported in clinical studies with upadacitinib.(1) |
RINVOQ, RINVOQ LQ |
| Inebilizumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Inebilizumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of inebilizumab with immunosuppressive or immunomodulating agents may result in myelosuppression including neutropenia resulting in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of inebilizumab states that the concurrent use of inebilizumab with immunosuppressive agents, including systemic corticosteroids, may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Inebilizumab has not been studied in combination with other immunosuppressants. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents. The most common infections reported by inebilizumab treated patients in the randomized and open-label clinical trial periods included urinary tract infections (20%), nasopharyngitis (13%), upper respiratory tract infections (8%), and influenza (7%). Although there been no cases of Hepatitis B virus reactivation or progressive multifocal leukoencephalopathy reported in patients taking inebilizumab, these infections have been observed in patients taking other B-cell-depleting antibodies.(1) |
UPLIZNA |
| Baricitinib/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Concurrent use of baricitinib with other biologic disease-modifying antirheumatic drugs (DMARDs) or potent immunosuppressants such as azathioprine or cyclosporine may result in additive or synergistic effects on the immune system. CLINICAL EFFECTS: Concurrent use of baricitinib with other biologic DMARDs or potent immunosuppressants such as azathioprine or cyclosporine may increase the risk of serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of baricitinib states that concurrent use of baricitinib with biologic DMARDs or potent immunosuppressants is not recommended.(1) DISCUSSION: Most patients who developed serious infections while being treated with baricitinib were on concomitant immunosuppressants like methotrexate and corticosteroids. The combination of baricitinib with other biologic DMARDs has not been studied.(1) |
OLUMIANT |
| Leflunomide; Teriflunomide/Selected Immunosuppressants SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Concurrent use of leflunomide or teriflunomide and potent immunosuppressants may result in additive or synergistic effects on the immune system.(1,2) Leflunomide is a prodrug and is converted to its active metabolite teriflunomide.(1) CLINICAL EFFECTS: Concurrent use of leflunomide or teriflunomide with immunosuppressants may result in an increased risk of serious infections, including opportunistic infections, especially Pneumocystis jiroveci pneumonia, tuberculosis (including extra-pulmonary tuberculosis), and aspergillosis. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: If leflunomide or teriflunomide is used concurrently with immunosuppressive agents, chronic CBC monitoring should be performed more frequently, every month instead of every 6 to 8 weeks. If bone marrow suppression or a serious infection occurs, leflunomide or teriflunomide should be stopped and rapid drug elimination procedure should be performed.(1,2) DISCUSSION: Pancytopenia, agranulocytosis and thrombocytopenia have been reported in patients receiving leflunomide or teriflunomide alone, but most frequently in patients taking concurrent immunosuppressants.(1,2) Severe and potentially fatal infections, including sepsis, have been reported in patients receiving leflunomide or teriflunomide, especially Pneumocystis jiroveci pneumonia and aspergillosis. Tuberculosis has also been reported.(1,2) |
ARAVA, AUBAGIO, LEFLUNICLO, LEFLUNOMIDE, TERIFLUNOMIDE |
| Ponesimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ponesimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ponesimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection, cryptococcal infection, or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The ponesimod US prescribing information states ponesimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Caution should be used during concomitant administration because of the risk of additive immune effects during therapy and in the weeks following administration. When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects. Initiating treatment with ponesimod after alemtuzumab is not recommended. However, ponesimod can generally be started immediately after discontinuation of beta interferon or glatiramer acetate.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections, cryptococcal meningitis, disseminated cryptococcal infections, and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1) |
PONVORY |
| Sodium Iodide I 131/Myelosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Sodium iodide I 131 can cause depression of the hematopoetic system. Myelosuppressives and immunomodulators also suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of sodium iodide I 131 with agents that cause bone marrow depression, including myelosuppressives or immunomodulators, may result in an enhanced risk of hematologic disorders, including anemia, blood dyscrasias, bone marrow depression, leukopenia, and thrombocytopenia. Bone marrow depression may increase the risk of serious infections and bleeding.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of sodium iodide I 131 states that concurrent use with bone marrow depressants may enhance the depression of the hematopoetic system caused by large doses of sodium iodide I 131.(1) Sodium iodide I 131 causes a dose-dependent bone marrow suppression, including neutropenia or thrombocytopenia, in the 3 to 5 weeks following administration. Patients may be at increased risk of infections or bleeding during this time. Monitor complete blood counts within one month of therapy. If results indicate leukopenia or thrombocytopenia, dosimetry should be used to determine a safe sodium iodide I 131 activity.(1) DISCUSSION: Hematologic disorders including death have been reported with sodium iodide I 131. The most common hematologic disorders reported include anemia, blood dyscrasias, bone marrow depression, leukopenia, and thrombocytopenia.(1) |
HICON, SODIUM IODIDE I-131 |
| Fingolimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Fingolimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1-3) CLINICAL EFFECTS: Concurrent use of fingolimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1-3) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: Recommendations for fingolimod regarding this interaction differ between regulatory approving agencies. The fingolimod US prescribing information states: - Antineoplastic, immune-modulating, or immunosuppressive therapies, (including corticosteroids) are expected to increase the risk of immunosuppression, and the risk of additive immune system effects must be considered if these therapies are coadministered with fingolimod. When switching from drugs with prolonged immune effects, such as natalizumab, teriflunomide or mitoxantrone, the duration and mode of action of these drugs must be considered to avoid unintended additive immunosuppressive effects when initiating fingolimod.(1) The fingolimod Canadian prescribing information states: - Concurrent use with immunosuppressive or immunomodulatory agents is contraindicated due to the risk of additive immune system effects. However, co-administration of a short course of corticosteroids (up to 5 days) did not increase the overall rate of infection in patients participating Phase III clinical trials.(2) The fingolimod UK specific product characteristics states: - Fingolimod is contraindicated in patients currently receiving immunosuppressive therapies or those immunocompromised by prior therapies. When switching patients from another disease modifying therapy to Gilenya, the half-life and mode of action of the other therapy must be considered in order to avoid an additive immune effect whilst at the same time minimizing the risk of disease activation.(3) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1-3) |
FINGOLIMOD, GILENYA, TASCENSO ODT |
| Ozanimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ozanimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ozanimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The ozanimod US prescribing information state this information regarding this interaction: -Ozanimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Caution should be used during concomitant administration because of the risk of additive immune effects during therapy and in the week following administration. When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects. Initiating treatment with ozanimod after alemtuzumab is not recommended. However, ozanimod can generally be started immediately after discontinuation of beta interferon or glatiramer acetate.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1) |
ZEPOSIA |
| Siponimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Siponimod in combination with immunosuppressives and immune-modulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of siponimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The siponimod US prescribing information state this information regarding this interaction: -Siponimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Caution should be used during concomitant administration because of the risk of additive immune effects during therapy and in the week following administration. When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects. Initiating treatment with siponimod after alemtuzumab is not recommended. However, siponimod can generally be started immediately after discontinuation of beta interferon or glatiramer acetate.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1) |
MAYZENT |
| Cladribine Oral/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Cladribine in combination with immunosuppressives and immune-modulators all suppress the immune system.(1-2) CLINICAL EFFECTS: Concurrent use of cladribine with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections, such as disseminated herpetic infection or progressive multifocal leukoencephalopathy (PML), an opportunistic infection caused by the JC virus (JCV).(1-2) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: Recommendations for cladribine regarding this interaction differ between regulatory approving agencies. The cladribine US prescribing information states: -Concomitant use with myelosuppressive or other immunosuppressive drugs is not recommended. Acute short-term therapy with corticosteroids can be administered. In patients who have previously been treated with immunomodulatory or immunosuppressive drugs, consider potential additive effect, the mode of action, and duration of effect of the other drugs prior to initiation of cladribine.(1) The cladribine Canadian prescribing information states: -Use of cladribine in immunocompromised patients is contraindicated because of a risk of additive effects on the immune system. Acute short-term therapy with corticosteroids can be administered during cladribine treatment.(2) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients who previously received immunomodulators or immunosuppressants.(1-2) |
CLADRIBINE, MAVENCLAD |
| Ritlecitinib/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ritlecitinib, immunosuppressives, and immunomodulators all suppress the immune system. CLINICAL EFFECTS: Concurrent use of ritlecitinib with immunosuppressives or immunomodulators may result in an increased risk of serious infections. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of ritlecitinib states that concurrent use of ritlecitinib with other JAK inhibitors, biologic immunomodulators, cyclosporine or other potent immunosuppressants is not recommended.(1) DISCUSSION: Serious infections have been reported in patients receiving ritlecitinib. Reported infections included appendicitis, COVID-19 infection (including pneumonia), and sepsis. Reports of viral reactivation, including herpes virus reactivation was reported in clinical studies with ritlecitinib.(1) |
LITFULO |
| Etrasimod/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Etrasimod causes reversible sequestration of lymphocytes in lymphoid tissues, resulting in a mean 55% decrease in peripheral blood lymphocyte count at 52 weeks.(1) Other immunosuppressives and immune-modulators also suppress the immune system. CLINICAL EFFECTS: Concurrent use of etrasimod with immunosuppressive or immune-modulating agents may result in an increased risk of serious and fatal infections, such as disseminated herpetic infection, cryptococcal infection, or progressive multifocal leukoencephalopathy (PML).(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications increases the risk of adverse effects. PATIENT MANAGEMENT: The etrasimod US prescribing information states etrasimod has not been studied in combination with anti-neoplastic, immune-modulating, or immunosuppressive therapies. Concomitant administration of these therapies with etrasimod should be avoided because of the risk of additive immune effects during therapy and in the weeks following administration. Etrasimod's effect on peripheral lymphocytes may persist for up to 5 weeks after discontinuation.(1) When switching from drugs with prolonged immune effects, the half-life and mode of action of these drugs must be considered in order to avoid unintended additive immunosuppressive effects.(1) DISCUSSION: Fatal disseminated herpes zoster and herpes simplex infections, cryptococcal meningitis, disseminated cryptococcal infections, and cases of progressive multifocal leukoencephalopathy (PML) have been reported in patients treated with other sphingosine-1 phosphate receptor modulators.(1) |
VELSIPITY |
| Ropeginterferon alfa-2b/Slt Immunosuppress; Immunomodulator SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Ropeginterferon alfa-2b and immunosuppressives both suppress the immune system. CLINICAL EFFECTS: Concurrent use of ropeginterferon alfa-2b with immunosuppressives may result in an increased risk of serious infections. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Avoid concurrent use of myelosuppressive agents.(1-2) If concurrent use cannot be avoided, monitor for effects of excessive immunosuppression. DISCUSSION: In clinical trials, 20% of patients experienced leukopenia. Interferon alfa products may cause fatal or life-threatening infections.(1-2) |
BESREMI, BESREMI PEN |
| Deuruxolitinib/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 2-Severe Interaction: Action is required to reduce the risk of severe adverse interaction. MECHANISM OF ACTION: Deuruxolitinib, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of deuruxolitinib and potent immunosuppressants may increase the risk of serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of deuruxolitinib states that concurrent use of deuruxolitinib with other JAK inhibitors, biologic immunomodulators, cyclosporine or other potent immunosuppressants is not recommended.(1) If concurrent use cannot be avoided, patients should be monitored for signs and symptoms of infection. If a patient develops a serious or opportunistic infection, interrupt deuruxolitinib treatment until the infection is controlled. DISCUSSION: Serious infections have been reported in patients receiving treatment with deuruxolitinib.(1) |
LEQSELVI |
There are 8 moderate interactions.
The clinician should assess the patient’s characteristics and take action as needed. Actions required for moderate interactions include, but are not limited to, discontinuing one or both agents, adjusting dosage, altering administration.
| Drug Interaction | Drug Names |
|---|---|
| Hydantoins/Selected Antineoplastics SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Antineoplastic agents may decrease the absorption and increase the metabolism of phenytoin. CLINICAL EFFECTS: The pharmacological effects of phenytoin may be decreased. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Monitor serum phenytoin concentrations when starting or discontinuing cancer chemotherapy. Adjust the dose of phenytoin as needed. DISCUSSION: Decreased plasma phenytoin concentrations and loss of seizure control have been reported after starting chemotherapy in patients receiving phenytoin. In order to maintain adequate levels of phenytoin during chemotherapy, it may be necessary to increase the dose of phenytoin. |
CEREBYX, DILANTIN, DILANTIN-125, FOSPHENYTOIN SODIUM, PHENYTEK, PHENYTOIN, PHENYTOIN SODIUM, PHENYTOIN SODIUM EXTENDED |
| Digoxin, Oral/Antineoplastics SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Decreased gastrointestinal digoxin absorption. CLINICAL EFFECTS: The pharmacologic effects of digoxin may be decreased. PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: Monitor serum digoxin concentrations and observe the patient for a decrease in pharmacologic activity. Adjust the dose of digoxin accordingly. Substituting digitoxin or digoxin capsules for digoxin tablets may circumvent this interaction. DISCUSSION: There are a number of factors affecting the outcome of this interaction. The effects of antineoplastic therapy on the gastrointestinal absorption of digoxin have only been studied with certain chemotherapeutic agents or regimens (e.g., bleomycin, carmustine, cyclophosphamide, cytarabine, doxorubicin, methotrexate, procarbazine, vincristine). The interaction appears to occur with the administration of oral digoxin tablets as opposed to digoxin capsules. The gastrointestinal absorption of digitoxin does not seem to be altered by antineoplastic therapy. |
DIGOXIN, LANOXIN |
| Ustekinumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Ustekinumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ustekinumab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of ustekinumab recommends caution because the concurrent use of ustekinumab with immunosuppressive agents may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Ustekinumab has not been studied in combination with other immunosuppressants in psoriasis studies. In psoriatic arthritis studies, concomitant methotrexate use did not appear to influence the safety or efficacy of ustekinumab. In Crohn's disease and ulcerative colitis studies, concomitant use of immunosuppressants or corticosteroids did not appear to influence the safety or efficacy of ustekinumab. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents.(1) The most common infections reported by ustekinumab treated patients in the clinical trial periods included nasopharyngitis(8%) and upper respiratory tract infection(5%). Serious bacterial, mycobacterial, fungal, and viral infections were observed in patients receiving ustekinumab. Cases of interstitial pneumonia, eosinophilic pneumonia, and cryptogenic organizing pneumonia resulting in respiratory failure or prolonged hospitalization have been reported in patients receiving ustekinumab.(1) |
IMULDOSA, OTULFI, PYZCHIVA, PYZCHIVA AUTOINJECTOR, SELARSDI, STARJEMZA, STELARA, STEQEYMA, USTEKINUMAB, USTEKINUMAB-AAUZ, USTEKINUMAB-AEKN, USTEKINUMAB-TTWE, WEZLANA, YESINTEK |
| COVID-19 Vaccines/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Immunosuppressants and immunomodulators may prevent the immune system from properly responding to the COVID-19 vaccine.(1-3) CLINICAL EFFECTS: Administration of a COVID-19 vaccine with immunosuppressants or immunomodulators may interfere with vaccine-induced immune response and impair the efficacy of the vaccine. However, patients should be offered and given a COVID-19 vaccine even if the use and timing of immunosuppressive agents cannot be adjusted.(1-3) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The Centers for Disease Control and Prevention (CDC),(1) Infectious Diseases Society of America (IDSA),(2) and the American College of Rheumatology (ACR)(3) have published guidances for COVID-19 vaccination in patients on immunosuppressants. The CDC states that all immunocompromised patients over 6 months of age should receive at least 1 dose of COVID-19 vaccine if eligible. See the CDC's Interim Clinical Considerations for Use of COVID-19 Vaccines for specific recommendations based on age, vaccination history, and vaccine manufacturer.(1) The CDC advises planning for vaccination at least 2 weeks before starting or resuming immunosuppressive therapy.(1) IDSA recommends timing COVID-19 vaccination at least 2 weeks before starting or at least 3 months after completing immunosuppressive therapy.(2) The ACR states that in general, immunosuppressants and immunomodulators should be held for 1-2 weeks after each vaccine dose.(3) Patients should be offered and given a COVID-19 vaccine even if the use and timing of immunosuppressive agents cannot be adjusted, though the immune response will likely be blunted. COVID-19 vaccines should not be delayed in patients taking immunosuppressive therapies.(1-2) See below for specific recommendations for certain agents. B-cell depleting agents, including rituximab: The CDC states that the utility of B-cell quantification to guide clinical care is not known and is not recommended. Patients who receive B-cell depleting therapy on a continuing basis should receive COVID-19 vaccines about 4 weeks before the next scheduled dose. For patients who received 1 or more doses of COVID-19 vaccine during treatment with B-cell-depleting therapies that were administered over a limited period (e.g., as part of a treatment regimen for certain malignancies), revaccination may be considered according to the current CDC recommendations for unvaccinated patients. The suggested interval to start revaccination is about 6 months after completion of the B-cell-depleting therapy.(1) IDSA recommends waiting for at least 3-6 months after the last infusion of B-cell depleting therapy before administering COVID-19 vaccines.(2) The ACR recommends consulting with the rheumatologist to determine optimal timing of COVID-19 vaccination. Measuring CD19 B cells may be considered to determine need for a booster vaccine dose. If B cell levels are not measured, a supplemental vaccine dose 2-4 weeks before the next scheduled dose of rituximab is recommended.(3) Recipients of hematopoietic cell transplant or CAR-T-cell therapy who received one or more doses of COVID-19 vaccine prior to or during treatment should undergo revaccination following the current CDC recommendations for unvaccinated patients. Revaccination should start at least 3 months (12 weeks) after transplant or CAR-T-cell therapy.(1,2) The CDC includes abatacept, cyclophosphamide, and TNF-alpha and cytokine inhibitors in their general recommendation to hold therapy for at least 2 weeks following vaccination (1) while the ACR provides different recommendations:(3) *Abatacept: - Subcutaneous abatacept should be withheld for 1-2 weeks after each vaccine dose, as disease activity allows. - For intravenous abatacept, time administration so that vaccination will occur 1 week before the next abatacept infusion. *Cyclophosphamide: When feasible, administer cyclophosphamide 1 week after each COVID-19 vaccine dose. *TNF-alpha inhibitors and cytokine inhibitors: The ACR was not able to reach consensus on whether to modify dosing or timing of these agents with COVID-19 vaccination. DISCUSSION: IDSA recommendations are based on cohort and case control studies in immunocompromised patients that found low to modest vaccine effectiveness (37-61%) but lower risks of COVID-19 association hospitalization, COVID-19 related mortality, and critical illness.(2) The ACR convened a COVID-19 Vaccine Guidance Task Force to provide guidance on optimal use of COVID-19 vaccines in rheumatology patients. These recommendations are based on limited clinical evidence of COVID-19 vaccines in patients without rheumatic and musculoskeletal disorders and evidence of other vaccines in this patient population.(3) The ACR recommendation for rituximab is based on studies of humoral immunity following receipt of other vaccines. These studies have uncertain generalizability to vaccination against COVID-19, as it is unknown if efficacy is attributable to induction of host T cells versus B cell (antibody-based) immunity.(3) The ACR recommendation for mycophenolate is based on preexisting data of mycophenolate on non-COVID-19 vaccine immunogenicity. Emerging data suggests that mycophenolate may impair SARS-CoV-2 vaccine response in rheumatic and musculoskeletal disease and transplant patients.(3) The ACR recommendation for methotrexate is based on data from influenza vaccines and pneumococcal vaccines with methotrexate.(3) The ACR recommendation for JAK inhibitors is based on concerns related to the effects of JAK inhibitors on interferon signaling that may result in a diminished vaccine response.(3) The ACR recommendation for subcutaneous abatacept is based on several studies suggesting a negative effect of abatacept on vaccine immunogenicity. The first vaccine dose primes naive T cells, naive T cell priming is inhibited by CTLA-4, and abatacept is a CTLA-4Ig construct. CTLA-4 should not inhibit boosts of already primed T cells at the time of the second vaccine dose.(3) |
COMIRNATY 2026-2027 (12Y UP), COMIRNATY 2026-2027(5-11Y), MNEXSPIKE 2026-2027 (12Y UP), NUVAXOVID 2026-2027, SPIKEVAX 2026-2027 (12Y UP), SPIKEVAX 2026-2027 (6M-11Y) |
| Sarilumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Sarilumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of sarilumab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of sarilumab recommends caution because the concurrent use of sarilumab with immunosuppressive agents may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Sarilumab was studied as monotherapy and in combination with methotrexate or conventional disease modifying antirheumatic drugs (DMARDs) in rheumatoid arthritis studies. Sarilumab has not been studied with biological DMARDs and concurrent use should be avoided. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents.(1) The most common infections reported by sarilumab treated patients in the clinical trial periods included pneumonia and cellulitis. Serious bacterial, mycobacterial, fungal, and viral infections were observed in patients receiving sarilumab. Cases of tuberculosis, candidiasis, and pneumocystis with sarilumab have been reported.(1) |
KEVZARA |
| Ublituximab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Ublituximab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of ublituximab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: The US manufacturer of ublituximab recommends caution because the concurrent use of ublituximab with immunomodulating or immunosuppressive agents, including immunosuppressant doses of corticosteroids, may increase the risk of infection.(1) If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents. When switching from agents with immune effects, the half-life and mechanism of action of these drugs must be taken into consideration in order to prevent additive immunosuppressive effects.(1) DISCUSSION: The most common infections reported by ublituximab-treated patients in the clinical trial periods included upper respiratory tract infections and urinary tract infections. Serious, including life-threatening or fatal, bacterial and viral infections were observed in patients receiving ublituximab.(1) Serious and/or fatal bacterial, fungal, and new or reactivated viral infections have been associated with other anti-CD20 B-cell depleting therapies. There were no cases of progressive multifocal leukoencephalopathy (PML) reported during the clinical trials; however, there have been reports of PML during or following completion of other anti-CD20 B-cell depleting therapies.(1) |
BRIUMVI |
| Tocilizumab/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Tocilizumab, immunosuppressives, and immunomodulators all suppress the immune system.(1) CLINICAL EFFECTS: Concurrent use of tocilizumab with immunosuppressive or immunomodulating agents may result in an increased risk for serious infections.(1) PREDISPOSING FACTORS: None determined. PATIENT MANAGEMENT: The US manufacturer of tocilizumab recommends caution because the concurrent use of tocilizumab with immunosuppressive agents may increase the risk of infection. If concurrent therapy is warranted, consider the risk of additive immune suppression and monitor based on prescribing information for both agents.(1) DISCUSSION: Tocilizumab was studied as monotherapy and in combination with methotrexate, non-biologic DMARDs or corticosteroids, depending on the indication. Tocilizumab has not been studied with biological DMARDs and concurrent use should be avoided. If concurrent therapy is warranted, consider the potential for increased immunosuppressive risks from both agents.(1) The most common infections reported by tocilizumab treated patients in the clinical trial periods included pneumonia, urinary tract infection, cellulitis, herpes zoster, gastroenteritis, diverticulitis, sepsis and bacterial arthritis. Serious bacterial, mycobacterial, fungal, and viral infections were observed in patients receiving tocilizumab. Cases of tuberculosis, cryptococcus, aspergillosis, candidiasis, and pneumocystosis have been reported.(1) |
ACTEMRA, ACTEMRA ACTPEN, AVTOZMA, AVTOZMA AUTOINJECTOR, TOFIDENCE, TYENNE, TYENNE AUTOINJECTOR |
| Cladribine Oncology Inj/Immunosuppressives; Immunomodulators SEVERITY LEVEL: 3-Moderate Interaction: Assess the risk to the patient and take action as needed. MECHANISM OF ACTION: Cladribine in combination with immunosuppressives and immune-modulators all suppress the immune system.(1-4) CLINICAL EFFECTS: Concurrent use of cladribine with immunosuppressive or immune-modulating agents may result in an increased risk of serious infections.(1-4) PREDISPOSING FACTORS: Incomplete washout of previously prescribed immunosuppressive or immune-modulating medications. PATIENT MANAGEMENT: Recommendations for cladribine regarding this interaction differ between regulatory approving agencies. The cladribine US, UK, and Australian prescribing information state: -Caution should be exercised if cladribine injection is administered before, after, or in conjunction with other drugs known to cause immunosuppression or myelosuppression.(1-3) The cladribine Canadian prescribing information states: -Proceed carefully in patients with severe bone marrow impairment of any etiology since further suppression of bone marrow function should be anticipated.(4) DISCUSSION: Severe bone marrow suppression, including neutropenia, anemia and thrombocytopenia, has been commonly observed in patients treated with cladribine injection, especially at high doses.(1-4) |
CLADRIBINE |
The following contraindication information is available for BLEOMYCIN SULFATE (bleomycin sulfate):
Drug contraindication overview.
No enhanced Contraindications information available for this drug.
No enhanced Contraindications information available for this drug.
There are 2 contraindications.
Absolute contraindication.
| Contraindication List |
|---|
| Lactation |
| Pulmonary fibrosis |
There are 7 severe contraindications.
Adequate patient monitoring is recommended for safer drug use.
| Severe List |
|---|
| Chronic kidney disease stage 3A (moderate) GFR 45-59 ml/min |
| Chronic kidney disease stage 3B (moderate) GFR 30-44 ml/min |
| Chronic kidney disease stage 4 (severe) GFR 15-29 ml/min |
| Chronic kidney disease stage 5 (failure) GFr<15 ml/min |
| Chronic obstructive pulmonary disease |
| Interstitial pneumonitis |
| Pregnancy |
There are 1 moderate contraindications.
Clinically significant contraindication, where the condition can be managed or treated before the drug may be given safely.
| Moderate List |
|---|
| Kidney disease with likely reduction in glomerular filtration rate (GFr) |
The following adverse reaction information is available for BLEOMYCIN SULFATE (bleomycin sulfate):
Adverse reaction overview.
No enhanced Common Adverse Effects information available for this drug.
No enhanced Common Adverse Effects information available for this drug.
There are 17 severe adverse reactions.
| More Frequent | Less Frequent |
|---|---|
|
Aphthous stomatitis Chills Fever Interstitial pneumonitis Pulmonary fibrosis Stomatitis |
Acute cognitive impairment Hypotension Wheezing |
| Rare/Very Rare |
|---|
|
Acute myocardial infarction Cerebral arteritis Cerebrovascular accident Drug-induced hepatitis Jaundice Pericardial effusion Renal failure Thrombotic thrombocytopenic purpura |
There are 5 less severe adverse reactions.
| More Frequent | Less Frequent |
|---|---|
|
Anorexia Skin rash Vomiting |
Alopecia Weight loss |
| Rare/Very Rare |
|---|
| None. |
The following precautions are available for BLEOMYCIN SULFATE (bleomycin sulfate):
No enhanced Pediatric Use information available for this drug.
Contraindicated
Severe Precaution
Management or Monitoring Precaution
Contraindicated
| None |
Severe Precaution
| None |
Management or Monitoring Precaution
| None |
Bleomycin sulfate can cause fetal toxicity when administered to pregnant women. The drug has been shown to be teratogenic in rats receiving intraperitoneal dosages of 1.5 mg/kg daily (about 1.6 times the recommended human dosage on a units/m2 basis) on days 6-15 of gestation.
Fetal malformations included skeletal defects, shortened innominate artery, and hydroureter. The drug has been shown to be abortifacient, but not teratogenic in rabbits receiving IV dosages of 1.2 mg/kg daily (about 2.4 times the recommended human dosage on a units/m2 basis) on days 6-18 of gestation.
There are no adequate and controlled studies to date using bleomycin sulfate in pregnant women. When the drug is administered during pregnancy or if the patient becomes pregnant while receiving the drug, the patient should be informed of the potential hazard to the fetus. Women of childbearing potential should be advised to avoid becoming pregnant during bleomycin sulfate therapy.
It is not known whether bleomycin is excreted in human milk. Because of the potential for serious adverse reactions to bleomycin in nursing infants if it were distributed, the manufacturer recommends that women receiving bleomycin discontinue nursing.
No enhanced Geriatric Use information available for this drug.
The following prioritized warning is available for BLEOMYCIN SULFATE (bleomycin sulfate):
WARNING: Rarely, bleomycin can cause a serious, allergic-like reaction. It is most common in lymphoma patients. Before your main treatment with this drug begins, your doctor may direct you to receive a smaller test dose to check for signs of this serious reaction.
Tell your doctor right away if any of the following serious side effects occur: dizziness/fainting, confusion, fever, chills, trouble breathing. Severe (sometimes fatal) lung problems (lung scarring) have rarely occurred in patients using this drug. This reaction is more likely in patients older than 70 years.
The risk of this reaction increases as you receive more doses of this drug. This problem may occur anytime during treatment. Tell your doctor right away if you experience any of these serious side effects: cough, fever, chills, chest pain, or difficult/painful breathing.
The following icd codes are available for BLEOMYCIN SULFATE (bleomycin sulfate)'s list of indications:
| Diffuse large b-cell lymphoma | |
| C83.3 | Diffuse large b-cell lymphoma |
| C83.30 | Diffuse large b-cell lymphoma, unspecified site |
| C83.31 | Diffuse large b-cell lymphoma, lymph nodes of head, face, and neck |
| C83.32 | Diffuse large b-cell lymphoma, intrathoracic lymph nodes |
| C83.33 | Diffuse large b-cell lymphoma, intra-abdominal lymph nodes |
| C83.34 | Diffuse large b-cell lymphoma, lymph nodes of axilla and upper limb |
| C83.35 | Diffuse large b-cell lymphoma, lymph nodes of inguinal region and lower limb |
| C83.36 | Diffuse large b-cell lymphoma, intrapelvic lymph nodes |
| C83.37 | Diffuse large b-cell lymphoma, spleen |
| C83.38 | Diffuse large b-cell lymphoma, lymph nodes of multiple sites |
| C83.39 | Diffuse large b-cell lymphoma, extranodal and solid organ sites |
| C83.398 | Diffuse large b-cell lymphoma of other extranodal and solid organ sites |
| Follicular lymphoma | |
| C82 | Follicular lymphoma |
| C82.0 | Follicular lymphoma grade I |
| C82.00 | Follicular lymphoma grade i, unspecified site |
| C82.01 | Follicular lymphoma grade i, lymph nodes of head, face, and neck |
| C82.02 | Follicular lymphoma grade i, intrathoracic lymph nodes |
| C82.03 | Follicular lymphoma grade i, intra-abdominal lymph nodes |
| C82.04 | Follicular lymphoma grade i, lymph nodes of axilla and upper limb |
| C82.05 | Follicular lymphoma grade i, lymph nodes of inguinal region and lower limb |
| C82.06 | Follicular lymphoma grade i, intrapelvic lymph nodes |
| C82.07 | Follicular lymphoma grade i, spleen |
| C82.08 | Follicular lymphoma grade i, lymph nodes of multiple sites |
| C82.09 | Follicular lymphoma grade i, extranodal and solid organ sites |
| C82.1 | Follicular lymphoma grade II |
| C82.10 | Follicular lymphoma grade Ii, unspecified site |
| C82.11 | Follicular lymphoma grade Ii, lymph nodes of head, face, and neck |
| C82.12 | Follicular lymphoma grade Ii, intrathoracic lymph nodes |
| C82.13 | Follicular lymphoma grade Ii, intra-abdominal lymph nodes |
| C82.14 | Follicular lymphoma grade Ii, lymph nodes of axilla and upper limb |
| C82.15 | Follicular lymphoma grade Ii, lymph nodes of inguinal region and lower limb |
| C82.16 | Follicular lymphoma grade Ii, intrapelvic lymph nodes |
| C82.17 | Follicular lymphoma grade Ii, spleen |
| C82.18 | Follicular lymphoma grade Ii, lymph nodes of multiple sites |
| C82.19 | Follicular lymphoma grade Ii, extranodal and solid organ sites |
| C82.2 | Follicular lymphoma grade IIi, unspecified |
| C82.20 | Follicular lymphoma grade IIi, unspecified, unspecified site |
| C82.21 | Follicular lymphoma grade IIi, unspecified, lymph nodes of head, face, and neck |
| C82.22 | Follicular lymphoma grade IIi, unspecified, intrathoracic lymph nodes |
| C82.23 | Follicular lymphoma grade IIi, unspecified, intra-abdominal lymph nodes |
| C82.24 | Follicular lymphoma grade IIi, unspecified, lymph nodes of axilla and upper limb |
| C82.25 | Follicular lymphoma grade IIi, unspecified, lymph nodes of inguinal region and lower limb |
| C82.26 | Follicular lymphoma grade IIi, unspecified, intrapelvic lymph nodes |
| C82.27 | Follicular lymphoma grade IIi, unspecified, spleen |
| C82.28 | Follicular lymphoma grade IIi, unspecified, lymph nodes of multiple sites |
| C82.29 | Follicular lymphoma grade IIi, unspecified, extranodal and solid organ sites |
| C82.3 | Follicular lymphoma grade IIia |
| C82.30 | Follicular lymphoma grade IIia, unspecified site |
| C82.31 | Follicular lymphoma grade IIia, lymph nodes of head, face, and neck |
| C82.32 | Follicular lymphoma grade IIia, intrathoracic lymph nodes |
| C82.33 | Follicular lymphoma grade IIia, intra-abdominal lymph nodes |
| C82.34 | Follicular lymphoma grade IIia, lymph nodes of axilla and upper limb |
| C82.35 | Follicular lymphoma grade IIia, lymph nodes of inguinal region and lower limb |
| C82.36 | Follicular lymphoma grade IIia, intrapelvic lymph nodes |
| C82.37 | Follicular lymphoma grade IIia, spleen |
| C82.38 | Follicular lymphoma grade IIia, lymph nodes of multiple sites |
| C82.39 | Follicular lymphoma grade IIia, extranodal and solid organ sites |
| C82.4 | Follicular lymphoma grade IIib |
| C82.40 | Follicular lymphoma grade IIib, unspecified site |
| C82.41 | Follicular lymphoma grade IIib, lymph nodes of head, face, and neck |
| C82.42 | Follicular lymphoma grade IIib, intrathoracic lymph nodes |
| C82.43 | Follicular lymphoma grade IIib, intra-abdominal lymph nodes |
| C82.44 | Follicular lymphoma grade IIib, lymph nodes of axilla and upper limb |
| C82.45 | Follicular lymphoma grade IIib, lymph nodes of inguinal region and lower limb |
| C82.46 | Follicular lymphoma grade IIib, intrapelvic lymph nodes |
| C82.47 | Follicular lymphoma grade IIib, spleen |
| C82.48 | Follicular lymphoma grade IIib, lymph nodes of multiple sites |
| C82.49 | Follicular lymphoma grade IIib, extranodal and solid organ sites |
| C82.5 | Diffuse follicle center lymphoma |
| C82.50 | Diffuse follicle center lymphoma, unspecified site |
| C82.51 | Diffuse follicle center lymphoma, lymph nodes of head, face, and neck |
| C82.52 | Diffuse follicle center lymphoma, intrathoracic lymph nodes |
| C82.53 | Diffuse follicle center lymphoma, intra-abdominal lymph nodes |
| C82.54 | Diffuse follicle center lymphoma, lymph nodes of axilla and upper limb |
| C82.55 | Diffuse follicle center lymphoma, lymph nodes of inguinal region and lower limb |
| C82.56 | Diffuse follicle center lymphoma, intrapelvic lymph nodes |
| C82.57 | Diffuse follicle center lymphoma, spleen |
| C82.58 | Diffuse follicle center lymphoma, lymph nodes of multiple sites |
| C82.59 | Diffuse follicle center lymphoma, extranodal and solid organ sites |
| C82.6 | Cutaneous follicle center lymphoma |
| C82.60 | Cutaneous follicle center lymphoma, unspecified site |
| C82.61 | Cutaneous follicle center lymphoma, lymph nodes of head, face, and neck |
| C82.62 | Cutaneous follicle center lymphoma, intrathoracic lymph nodes |
| C82.63 | Cutaneous follicle center lymphoma, intra-abdominal lymph nodes |
| C82.64 | Cutaneous follicle center lymphoma, lymph nodes of axilla and upper limb |
| C82.65 | Cutaneous follicle center lymphoma, lymph nodes of inguinal region and lower limb |
| C82.66 | Cutaneous follicle center lymphoma, intrapelvic lymph nodes |
| C82.67 | Cutaneous follicle center lymphoma, spleen |
| C82.68 | Cutaneous follicle center lymphoma, lymph nodes of multiple sites |
| C82.69 | Cutaneous follicle center lymphoma, extranodal and solid organ sites |
| C82.8 | Other types of follicular lymphoma |
| C82.80 | Other types of follicular lymphoma, unspecified site |
| C82.81 | Other types of follicular lymphoma, lymph nodes of head, face, and neck |
| C82.82 | Other types of follicular lymphoma, intrathoracic lymph nodes |
| C82.83 | Other types of follicular lymphoma, intra-abdominal lymph nodes |
| C82.84 | Other types of follicular lymphoma, lymph nodes of axilla and upper limb |
| C82.85 | Other types of follicular lymphoma, lymph nodes of inguinal region and lower limb |
| C82.86 | Other types of follicular lymphoma, intrapelvic lymph nodes |
| C82.87 | Other types of follicular lymphoma, spleen |
| C82.88 | Other types of follicular lymphoma, lymph nodes of multiple sites |
| C82.89 | Other types of follicular lymphoma, extranodal and solid organ sites |
| C82.9 | Follicular lymphoma, unspecified |
| C82.90 | Follicular lymphoma, unspecified, unspecified site |
| C82.91 | Follicular lymphoma, unspecified, lymph nodes of head, face, and neck |
| C82.92 | Follicular lymphoma, unspecified, intrathoracic lymph nodes |
| C82.93 | Follicular lymphoma, unspecified, intra-abdominal lymph nodes |
| C82.94 | Follicular lymphoma, unspecified, lymph nodes of axilla and upper limb |
| C82.95 | Follicular lymphoma, unspecified, lymph nodes of inguinal region and lower limb |
| C82.96 | Follicular lymphoma, unspecified, intrapelvic lymph nodes |
| C82.97 | Follicular lymphoma, unspecified, spleen |
| C82.98 | Follicular lymphoma, unspecified, lymph nodes of multiple sites |
| C82.99 | Follicular lymphoma, unspecified, extranodal and solid organ sites |
| Hodgkin's lymphoma | |
| C81 | Hodgkin lymphoma |
| C81.0 | Nodular lymphocyte predominant hodgkin lymphoma |
| C81.00 | Nodular lymphocyte predominant hodgkin lymphoma, unspecified site |
| C81.01 | Nodular lymphocyte predominant hodgkin lymphoma, lymph nodes of head, face, and neck |
| C81.02 | Nodular lymphocyte predominant hodgkin lymphoma, intrathoracic lymph nodes |
| C81.03 | Nodular lymphocyte predominant hodgkin lymphoma, intra-abdominal lymph nodes |
| C81.04 | Nodular lymphocyte predominant hodgkin lymphoma, lymph nodes of axilla and upper limb |
| C81.05 | Nodular lymphocyte predominant hodgkin lymphoma, lymph nodes of inguinal region and lower limb |
| C81.06 | Nodular lymphocyte predominant hodgkin lymphoma, intrapelvic lymph nodes |
| C81.07 | Nodular lymphocyte predominant hodgkin lymphoma, spleen |
| C81.08 | Nodular lymphocyte predominant hodgkin lymphoma, lymph nodes of multiple sites |
| C81.09 | Nodular lymphocyte predominant hodgkin lymphoma, extranodal and solid organ sites |
| C81.1 | Nodular sclerosis hodgkin lymphoma |
| C81.10 | Nodular sclerosis hodgkin lymphoma, unspecified site |
| C81.11 | Nodular sclerosis hodgkin lymphoma, lymph nodes of head, face, and neck |
| C81.12 | Nodular sclerosis hodgkin lymphoma, intrathoracic lymph nodes |
| C81.13 | Nodular sclerosis hodgkin lymphoma, intra-abdominal lymph nodes |
| C81.14 | Nodular sclerosis hodgkin lymphoma, lymph nodes of axilla and upper limb |
| C81.15 | Nodular sclerosis hodgkin lymphoma, lymph nodes of inguinal region and lower limb |
| C81.16 | Nodular sclerosis hodgkin lymphoma, intrapelvic lymph nodes |
| C81.17 | Nodular sclerosis hodgkin lymphoma, spleen |
| C81.18 | Nodular sclerosis hodgkin lymphoma, lymph nodes of multiple sites |
| C81.19 | Nodular sclerosis hodgkin lymphoma, extranodal and solid organ sites |
| C81.2 | Mixed cellularity hodgkin lymphoma |
| C81.20 | Mixed cellularity hodgkin lymphoma, unspecified site |
| C81.21 | Mixed cellularity hodgkin lymphoma, lymph nodes of head, face, and neck |
| C81.22 | Mixed cellularity hodgkin lymphoma, intrathoracic lymph nodes |
| C81.23 | Mixed cellularity hodgkin lymphoma, intra-abdominal lymph nodes |
| C81.24 | Mixed cellularity hodgkin lymphoma, lymph nodes of axilla and upper limb |
| C81.25 | Mixed cellularity hodgkin lymphoma, lymph nodes of inguinal region and lower limb |
| C81.26 | Mixed cellularity hodgkin lymphoma, intrapelvic lymph nodes |
| C81.27 | Mixed cellularity hodgkin lymphoma, spleen |
| C81.28 | Mixed cellularity hodgkin lymphoma, lymph nodes of multiple sites |
| C81.29 | Mixed cellularity hodgkin lymphoma, extranodal and solid organ sites |
| C81.3 | Lymphocyte depleted hodgkin lymphoma |
| C81.30 | Lymphocyte depleted hodgkin lymphoma, unspecified site |
| C81.31 | Lymphocyte depleted hodgkin lymphoma, lymph nodes of head, face, and neck |
| C81.32 | Lymphocyte depleted hodgkin lymphoma, intrathoracic lymph nodes |
| C81.33 | Lymphocyte depleted hodgkin lymphoma, intra-abdominal lymph nodes |
| C81.34 | Lymphocyte depleted hodgkin lymphoma, lymph nodes of axilla and upper limb |
| C81.35 | Lymphocyte depleted hodgkin lymphoma, lymph nodes of inguinal region and lower limb |
| C81.36 | Lymphocyte depleted hodgkin lymphoma, intrapelvic lymph nodes |
| C81.37 | Lymphocyte depleted hodgkin lymphoma, spleen |
| C81.38 | Lymphocyte depleted hodgkin lymphoma, lymph nodes of multiple sites |
| C81.39 | Lymphocyte depleted hodgkin lymphoma, extranodal and solid organ sites |
| C81.4 | Lymphocyte-rich hodgkin lymphoma |
| C81.40 | Lymphocyte-rich hodgkin lymphoma, unspecified site |
| C81.41 | Lymphocyte-rich hodgkin lymphoma, lymph nodes of head, face, and neck |
| C81.42 | Lymphocyte-rich hodgkin lymphoma, intrathoracic lymph nodes |
| C81.43 | Lymphocyte-rich hodgkin lymphoma, intra-abdominal lymph nodes |
| C81.44 | Lymphocyte-rich hodgkin lymphoma, lymph nodes of axilla and upper limb |
| C81.45 | Lymphocyte-rich hodgkin lymphoma, lymph nodes of inguinal region and lower limb |
| C81.46 | Lymphocyte-rich hodgkin lymphoma, intrapelvic lymph nodes |
| C81.47 | Lymphocyte-rich hodgkin lymphoma, spleen |
| C81.48 | Lymphocyte-rich hodgkin lymphoma, lymph nodes of multiple sites |
| C81.49 | Lymphocyte-rich hodgkin lymphoma, extranodal and solid organ sites |
| C81.7 | Other hodgkin lymphoma |
| C81.70 | Other hodgkin lymphoma, unspecified site |
| C81.71 | Other hodgkin lymphoma, lymph nodes of head, face, and neck |
| C81.72 | Other hodgkin lymphoma, intrathoracic lymph nodes |
| C81.73 | Other hodgkin lymphoma, intra-abdominal lymph nodes |
| C81.74 | Other hodgkin lymphoma, lymph nodes of axilla and upper limb |
| C81.75 | Other hodgkin lymphoma, lymph nodes of inguinal region and lower limb |
| C81.76 | Other hodgkin lymphoma, intrapelvic lymph nodes |
| C81.77 | Other hodgkin lymphoma, spleen |
| C81.78 | Other hodgkin lymphoma, lymph nodes of multiple sites |
| C81.79 | Other hodgkin lymphoma, extranodal and solid organ sites |
| C81.9 | Hodgkin lymphoma, unspecified |
| C81.90 | Hodgkin lymphoma, unspecified, unspecified site |
| C81.91 | Hodgkin lymphoma, unspecified, lymph nodes of head, face, and neck |
| C81.92 | Hodgkin lymphoma, unspecified, intrathoracic lymph nodes |
| C81.93 | Hodgkin lymphoma, unspecified, intra-abdominal lymph nodes |
| C81.94 | Hodgkin lymphoma, unspecified, lymph nodes of axilla and upper limb |
| C81.95 | Hodgkin lymphoma, unspecified, lymph nodes of inguinal region and lower limb |
| C81.96 | Hodgkin lymphoma, unspecified, intrapelvic lymph nodes |
| C81.97 | Hodgkin lymphoma, unspecified, spleen |
| C81.98 | Hodgkin lymphoma, unspecified, lymph nodes of multiple sites |
| C81.99 | Hodgkin lymphoma, unspecified, extranodal and solid organ sites |
| Non-hodgkin's lymphoma | |
| C82 | Follicular lymphoma |
| C82.0 | Follicular lymphoma grade I |
| C82.00 | Follicular lymphoma grade i, unspecified site |
| C82.01 | Follicular lymphoma grade i, lymph nodes of head, face, and neck |
| C82.02 | Follicular lymphoma grade i, intrathoracic lymph nodes |
| C82.03 | Follicular lymphoma grade i, intra-abdominal lymph nodes |
| C82.04 | Follicular lymphoma grade i, lymph nodes of axilla and upper limb |
| C82.05 | Follicular lymphoma grade i, lymph nodes of inguinal region and lower limb |
| C82.06 | Follicular lymphoma grade i, intrapelvic lymph nodes |
| C82.07 | Follicular lymphoma grade i, spleen |
| C82.08 | Follicular lymphoma grade i, lymph nodes of multiple sites |
| C82.09 | Follicular lymphoma grade i, extranodal and solid organ sites |
| C82.1 | Follicular lymphoma grade II |
| C82.10 | Follicular lymphoma grade Ii, unspecified site |
| C82.11 | Follicular lymphoma grade Ii, lymph nodes of head, face, and neck |
| C82.12 | Follicular lymphoma grade Ii, intrathoracic lymph nodes |
| C82.13 | Follicular lymphoma grade Ii, intra-abdominal lymph nodes |
| C82.14 | Follicular lymphoma grade Ii, lymph nodes of axilla and upper limb |
| C82.15 | Follicular lymphoma grade Ii, lymph nodes of inguinal region and lower limb |
| C82.16 | Follicular lymphoma grade Ii, intrapelvic lymph nodes |
| C82.17 | Follicular lymphoma grade Ii, spleen |
| C82.18 | Follicular lymphoma grade Ii, lymph nodes of multiple sites |
| C82.19 | Follicular lymphoma grade Ii, extranodal and solid organ sites |
| C82.2 | Follicular lymphoma grade IIi, unspecified |
| C82.20 | Follicular lymphoma grade IIi, unspecified, unspecified site |
| C82.21 | Follicular lymphoma grade IIi, unspecified, lymph nodes of head, face, and neck |
| C82.22 | Follicular lymphoma grade IIi, unspecified, intrathoracic lymph nodes |
| C82.23 | Follicular lymphoma grade IIi, unspecified, intra-abdominal lymph nodes |
| C82.24 | Follicular lymphoma grade IIi, unspecified, lymph nodes of axilla and upper limb |
| C82.25 | Follicular lymphoma grade IIi, unspecified, lymph nodes of inguinal region and lower limb |
| C82.26 | Follicular lymphoma grade IIi, unspecified, intrapelvic lymph nodes |
| C82.27 | Follicular lymphoma grade IIi, unspecified, spleen |
| C82.28 | Follicular lymphoma grade IIi, unspecified, lymph nodes of multiple sites |
| C82.29 | Follicular lymphoma grade IIi, unspecified, extranodal and solid organ sites |
| C82.3 | Follicular lymphoma grade IIia |
| C82.30 | Follicular lymphoma grade IIia, unspecified site |
| C82.31 | Follicular lymphoma grade IIia, lymph nodes of head, face, and neck |
| C82.32 | Follicular lymphoma grade IIia, intrathoracic lymph nodes |
| C82.33 | Follicular lymphoma grade IIia, intra-abdominal lymph nodes |
| C82.34 | Follicular lymphoma grade IIia, lymph nodes of axilla and upper limb |
| C82.35 | Follicular lymphoma grade IIia, lymph nodes of inguinal region and lower limb |
| C82.36 | Follicular lymphoma grade IIia, intrapelvic lymph nodes |
| C82.37 | Follicular lymphoma grade IIia, spleen |
| C82.38 | Follicular lymphoma grade IIia, lymph nodes of multiple sites |
| C82.39 | Follicular lymphoma grade IIia, extranodal and solid organ sites |
| C82.4 | Follicular lymphoma grade IIib |
| C82.40 | Follicular lymphoma grade IIib, unspecified site |
| C82.41 | Follicular lymphoma grade IIib, lymph nodes of head, face, and neck |
| C82.42 | Follicular lymphoma grade IIib, intrathoracic lymph nodes |
| C82.43 | Follicular lymphoma grade IIib, intra-abdominal lymph nodes |
| C82.44 | Follicular lymphoma grade IIib, lymph nodes of axilla and upper limb |
| C82.45 | Follicular lymphoma grade IIib, lymph nodes of inguinal region and lower limb |
| C82.46 | Follicular lymphoma grade IIib, intrapelvic lymph nodes |
| C82.47 | Follicular lymphoma grade IIib, spleen |
| C82.48 | Follicular lymphoma grade IIib, lymph nodes of multiple sites |
| C82.49 | Follicular lymphoma grade IIib, extranodal and solid organ sites |
| C82.5 | Diffuse follicle center lymphoma |
| C82.50 | Diffuse follicle center lymphoma, unspecified site |
| C82.51 | Diffuse follicle center lymphoma, lymph nodes of head, face, and neck |
| C82.52 | Diffuse follicle center lymphoma, intrathoracic lymph nodes |
| C82.53 | Diffuse follicle center lymphoma, intra-abdominal lymph nodes |
| C82.54 | Diffuse follicle center lymphoma, lymph nodes of axilla and upper limb |
| C82.55 | Diffuse follicle center lymphoma, lymph nodes of inguinal region and lower limb |
| C82.56 | Diffuse follicle center lymphoma, intrapelvic lymph nodes |
| C82.57 | Diffuse follicle center lymphoma, spleen |
| C82.58 | Diffuse follicle center lymphoma, lymph nodes of multiple sites |
| C82.59 | Diffuse follicle center lymphoma, extranodal and solid organ sites |
| C82.6 | Cutaneous follicle center lymphoma |
| C82.60 | Cutaneous follicle center lymphoma, unspecified site |
| C82.61 | Cutaneous follicle center lymphoma, lymph nodes of head, face, and neck |
| C82.62 | Cutaneous follicle center lymphoma, intrathoracic lymph nodes |
| C82.63 | Cutaneous follicle center lymphoma, intra-abdominal lymph nodes |
| C82.64 | Cutaneous follicle center lymphoma, lymph nodes of axilla and upper limb |
| C82.65 | Cutaneous follicle center lymphoma, lymph nodes of inguinal region and lower limb |
| C82.66 | Cutaneous follicle center lymphoma, intrapelvic lymph nodes |
| C82.67 | Cutaneous follicle center lymphoma, spleen |
| C82.68 | Cutaneous follicle center lymphoma, lymph nodes of multiple sites |
| C82.69 | Cutaneous follicle center lymphoma, extranodal and solid organ sites |
| C82.8 | Other types of follicular lymphoma |
| C82.80 | Other types of follicular lymphoma, unspecified site |
| C82.81 | Other types of follicular lymphoma, lymph nodes of head, face, and neck |
| C82.82 | Other types of follicular lymphoma, intrathoracic lymph nodes |
| C82.83 | Other types of follicular lymphoma, intra-abdominal lymph nodes |
| C82.84 | Other types of follicular lymphoma, lymph nodes of axilla and upper limb |
| C82.85 | Other types of follicular lymphoma, lymph nodes of inguinal region and lower limb |
| C82.86 | Other types of follicular lymphoma, intrapelvic lymph nodes |
| C82.87 | Other types of follicular lymphoma, spleen |
| C82.88 | Other types of follicular lymphoma, lymph nodes of multiple sites |
| C82.89 | Other types of follicular lymphoma, extranodal and solid organ sites |
| C82.9 | Follicular lymphoma, unspecified |
| C82.90 | Follicular lymphoma, unspecified, unspecified site |
| C82.91 | Follicular lymphoma, unspecified, lymph nodes of head, face, and neck |
| C82.92 | Follicular lymphoma, unspecified, intrathoracic lymph nodes |
| C82.93 | Follicular lymphoma, unspecified, intra-abdominal lymph nodes |
| C82.94 | Follicular lymphoma, unspecified, lymph nodes of axilla and upper limb |
| C82.95 | Follicular lymphoma, unspecified, lymph nodes of inguinal region and lower limb |
| C82.96 | Follicular lymphoma, unspecified, intrapelvic lymph nodes |
| C82.97 | Follicular lymphoma, unspecified, spleen |
| C82.98 | Follicular lymphoma, unspecified, lymph nodes of multiple sites |
| C82.99 | Follicular lymphoma, unspecified, extranodal and solid organ sites |
| C83 | Non-follicular lymphoma |
| C83.0 | Small cell b-cell lymphoma |
| C83.00 | Small cell b-cell lymphoma, unspecified site |
| C83.01 | Small cell b-cell lymphoma, lymph nodes of head, face, and neck |
| C83.02 | Small cell b-cell lymphoma, intrathoracic lymph nodes |
| C83.03 | Small cell b-cell lymphoma, intra-abdominal lymph nodes |
| C83.04 | Small cell b-cell lymphoma, lymph nodes of axilla and upper limb |
| C83.05 | Small cell b-cell lymphoma, lymph nodes of inguinal region and lower limb |
| C83.06 | Small cell b-cell lymphoma, intrapelvic lymph nodes |
| C83.07 | Small cell b-cell lymphoma, spleen |
| C83.08 | Small cell b-cell lymphoma, lymph nodes of multiple sites |
| C83.09 | Small cell b-cell lymphoma, extranodal and solid organ sites |
| C83.1 | Mantle cell lymphoma |
| C83.10 | Mantle cell lymphoma, unspecified site |
| C83.11 | Mantle cell lymphoma, lymph nodes of head, face, and neck |
| C83.12 | Mantle cell lymphoma, intrathoracic lymph nodes |
| C83.13 | Mantle cell lymphoma, intra-abdominal lymph nodes |
| C83.14 | Mantle cell lymphoma, lymph nodes of axilla and upper limb |
| C83.15 | Mantle cell lymphoma, lymph nodes of inguinal region and lower limb |
| C83.16 | Mantle cell lymphoma, intrapelvic lymph nodes |
| C83.17 | Mantle cell lymphoma, spleen |
| C83.18 | Mantle cell lymphoma, lymph nodes of multiple sites |
| C83.19 | Mantle cell lymphoma, extranodal and solid organ sites |
| C83.3 | Diffuse large b-cell lymphoma |
| C83.30 | Diffuse large b-cell lymphoma, unspecified site |
| C83.31 | Diffuse large b-cell lymphoma, lymph nodes of head, face, and neck |
| C83.32 | Diffuse large b-cell lymphoma, intrathoracic lymph nodes |
| C83.33 | Diffuse large b-cell lymphoma, intra-abdominal lymph nodes |
| C83.34 | Diffuse large b-cell lymphoma, lymph nodes of axilla and upper limb |
| C83.35 | Diffuse large b-cell lymphoma, lymph nodes of inguinal region and lower limb |
| C83.36 | Diffuse large b-cell lymphoma, intrapelvic lymph nodes |
| C83.37 | Diffuse large b-cell lymphoma, spleen |
| C83.38 | Diffuse large b-cell lymphoma, lymph nodes of multiple sites |
| C83.39 | Diffuse large b-cell lymphoma, extranodal and solid organ sites |
| C83.5 | Lymphoblastic (diffuse) lymphoma |
| C83.50 | Lymphoblastic (diffuse) lymphoma, unspecified site |
| C83.51 | Lymphoblastic (diffuse) lymphoma, lymph nodes of head, face, and neck |
| C83.52 | Lymphoblastic (diffuse) lymphoma, intrathoracic lymph nodes |
| C83.53 | Lymphoblastic (diffuse) lymphoma, intra-abdominal lymph nodes |
| C83.54 | Lymphoblastic (diffuse) lymphoma, lymph nodes of axilla and upper limb |
| C83.55 | Lymphoblastic (diffuse) lymphoma, lymph nodes of inguinal region and lower limb |
| C83.56 | Lymphoblastic (diffuse) lymphoma, intrapelvic lymph nodes |
| C83.57 | Lymphoblastic (diffuse) lymphoma, spleen |
| C83.58 | Lymphoblastic (diffuse) lymphoma, lymph nodes of multiple sites |
| C83.59 | Lymphoblastic (diffuse) lymphoma, extranodal and solid organ sites |
| C83.7 | Burkitt lymphoma |
| C83.70 | Burkitt lymphoma, unspecified site |
| C83.71 | Burkitt lymphoma, lymph nodes of head, face, and neck |
| C83.72 | Burkitt lymphoma, intrathoracic lymph nodes |
| C83.73 | Burkitt lymphoma, intra-abdominal lymph nodes |
| C83.74 | Burkitt lymphoma, lymph nodes of axilla and upper limb |
| C83.75 | Burkitt lymphoma, lymph nodes of inguinal region and lower limb |
| C83.76 | Burkitt lymphoma, intrapelvic lymph nodes |
| C83.77 | Burkitt lymphoma, spleen |
| C83.78 | Burkitt lymphoma, lymph nodes of multiple sites |
| C83.79 | Burkitt lymphoma, extranodal and solid organ sites |
| C83.8 | Other non-follicular lymphoma |
| C83.80 | Other non-follicular lymphoma, unspecified site |
| C83.81 | Other non-follicular lymphoma, lymph nodes of head, face, and neck |
| C83.82 | Other non-follicular lymphoma, intrathoracic lymph nodes |
| C83.83 | Other non-follicular lymphoma, intra-abdominal lymph nodes |
| C83.84 | Other non-follicular lymphoma, lymph nodes of axilla and upper limb |
| C83.85 | Other non-follicular lymphoma, lymph nodes of inguinal region and lower limb |
| C83.86 | Other non-follicular lymphoma, intrapelvic lymph nodes |
| C83.87 | Other non-follicular lymphoma, spleen |
| C83.88 | Other non-follicular lymphoma, lymph nodes of multiple sites |
| C83.89 | Other non-follicular lymphoma, extranodal and solid organ sites |
| C83.9 | Non-follicular (diffuse) lymphoma, unspecified |
| C83.90 | Non-follicular (diffuse) lymphoma, unspecified, unspecified site |
| C83.91 | Non-follicular (diffuse) lymphoma, unspecified, lymph nodes of head, face, and neck |
| C83.92 | Non-follicular (diffuse) lymphoma, unspecified, intrathoracic lymph nodes |
| C83.93 | Non-follicular (diffuse) lymphoma, unspecified, intra-abdominal lymph nodes |
| C83.94 | Non-follicular (diffuse) lymphoma, unspecified, lymph nodes of axilla and upper limb |
| C83.95 | Non-follicular (diffuse) lymphoma, unspecified, lymph nodes of inguinal region and lower limb |
| C83.96 | Non-follicular (diffuse) lymphoma, unspecified, intrapelvic lymph nodes |
| C83.97 | Non-follicular (diffuse) lymphoma, unspecified, spleen |
| C83.98 | Non-follicular (diffuse) lymphoma, unspecified, lymph nodes of multiple sites |
| C83.99 | Non-follicular (diffuse) lymphoma, unspecified, extranodal and solid organ sites |
| C84 | Mature t/Nk-cell lymphomas |
| C84.0 | Mycosis fungoides |
| C84.00 | Mycosis fungoides, unspecified site |
| C84.01 | Mycosis fungoides, lymph nodes of head, face, and neck |
| C84.02 | Mycosis fungoides, intrathoracic lymph nodes |
| C84.03 | Mycosis fungoides, intra-abdominal lymph nodes |
| C84.04 | Mycosis fungoides, lymph nodes of axilla and upper limb |
| C84.05 | Mycosis fungoides, lymph nodes of inguinal region and lower limb |
| C84.06 | Mycosis fungoides, intrapelvic lymph nodes |
| C84.07 | Mycosis fungoides, spleen |
| C84.08 | Mycosis fungoides, lymph nodes of multiple sites |
| C84.09 | Mycosis fungoides, extranodal and solid organ sites |
| C84.1 | Sezary disease |
| C84.10 | Sezary disease, unspecified site |
| C84.11 | Sezary disease, lymph nodes of head, face, and neck |
| C84.12 | Sezary disease, intrathoracic lymph nodes |
| C84.13 | Sezary disease, intra-abdominal lymph nodes |
| C84.14 | Sezary disease, lymph nodes of axilla and upper limb |
| C84.15 | Sezary disease, lymph nodes of inguinal region and lower limb |
| C84.16 | Sezary disease, intrapelvic lymph nodes |
| C84.17 | Sezary disease, spleen |
| C84.18 | Sezary disease, lymph nodes of multiple sites |
| C84.19 | Sezary disease, extranodal and solid organ sites |
| C84.4 | Peripheral t-cell lymphoma, not elsewhere classified |
| C84.40 | Peripheral t-cell lymphoma, not elsewhere classified, unspecified site |
| C84.41 | Peripheral t-cell lymphoma, not elsewhere classified, lymph nodes of head, face, and neck |
| C84.42 | Peripheral t-cell lymphoma, not elsewhere classified, intrathoracic lymph nodes |
| C84.43 | Peripheral t-cell lymphoma, not elsewhere classified, intra-abdominal lymph nodes |
| C84.44 | Peripheral t-cell lymphoma, not elsewhere classified, lymph nodes of axilla and upper limb |
| C84.45 | Peripheral t-cell lymphoma, not elsewhere classified, lymph nodes of inguinal region and lower limb |
| C84.46 | Peripheral t-cell lymphoma, not elsewhere classified, intrapelvic lymph nodes |
| C84.47 | Peripheral t-cell lymphoma, not elsewhere classified, spleen |
| C84.48 | Peripheral t-cell lymphoma, not elsewhere classified, lymph nodes of multiple sites |
| C84.49 | Peripheral t-cell lymphoma, not elsewhere classified, extranodal and solid organ sites |
| C84.6 | Anaplastic large cell lymphoma, ALk-positive |
| C84.60 | Anaplastic large cell lymphoma, ALk-positive, unspecified site |
| C84.61 | Anaplastic large cell lymphoma, ALk-positive, lymph nodes of head, face, and neck |
| C84.62 | Anaplastic large cell lymphoma, ALk-positive, intrathoracic lymph nodes |
| C84.63 | Anaplastic large cell lymphoma, ALk-positive, intra-abdominal lymph nodes |
| C84.64 | Anaplastic large cell lymphoma, ALk-positive, lymph nodes of axilla and upper limb |
| C84.65 | Anaplastic large cell lymphoma, ALk-positive, lymph nodes of inguinal region and lower limb |
| C84.66 | Anaplastic large cell lymphoma, ALk-positive, intrapelvic lymph nodes |
| C84.67 | Anaplastic large cell lymphoma, ALk-positive, spleen |
| C84.68 | Anaplastic large cell lymphoma, ALk-positive, lymph nodes of multiple sites |
| C84.69 | Anaplastic large cell lymphoma, ALk-positive, extranodal and solid organ sites |
| C84.7 | Anaplastic large cell lymphoma, ALk-negative |
| C84.70 | Anaplastic large cell lymphoma, ALk-negative, unspecified site |
| C84.71 | Anaplastic large cell lymphoma, ALk-negative, lymph nodes of head, face, and neck |
| C84.72 | Anaplastic large cell lymphoma, ALk-negative, intrathoracic lymph nodes |
| C84.73 | Anaplastic large cell lymphoma, ALk-negative, intra-abdominal lymph nodes |
| C84.74 | Anaplastic large cell lymphoma, ALk-negative, lymph nodes of axilla and upper limb |
| C84.75 | Anaplastic large cell lymphoma, ALk-negative, lymph nodes of inguinal region and lower limb |
| C84.76 | Anaplastic large cell lymphoma, ALk-negative, intrapelvic lymph nodes |
| C84.77 | Anaplastic large cell lymphoma, ALk-negative, spleen |
| C84.78 | Anaplastic large cell lymphoma, ALk-negative, lymph nodes of multiple sites |
| C84.79 | Anaplastic large cell lymphoma, ALk-negative, extranodal and solid organ sites |
| C84.7A | Anaplastic large cell lymphoma, ALk-negative, breast |
| C84.9 | Mature t/Nk-cell lymphomas, unspecified |
| C84.90 | Mature t/Nk-cell lymphomas, unspecified, unspecified site |
| C84.91 | Mature t/Nk-cell lymphomas, unspecified, lymph nodes of head, face, and neck |
| C84.92 | Mature t/Nk-cell lymphomas, unspecified, intrathoracic lymph nodes |
| C84.93 | Mature t/Nk-cell lymphomas, unspecified, intra-abdominal lymph nodes |
| C84.94 | Mature t/Nk-cell lymphomas, unspecified, lymph nodes of axilla and upper limb |
| C84.95 | Mature t/Nk-cell lymphomas, unspecified, lymph nodes of inguinal region and lower limb |
| C84.96 | Mature t/Nk-cell lymphomas, unspecified, intrapelvic lymph nodes |
| C84.97 | Mature t/Nk-cell lymphomas, unspecified, spleen |
| C84.98 | Mature t/Nk-cell lymphomas, unspecified, lymph nodes of multiple sites |
| C84.99 | Mature t/Nk-cell lymphomas, unspecified, extranodal and solid organ sites |
| C84.A | Cutaneous t-cell lymphoma, unspecified |
| C84.A0 | Cutaneous t-cell lymphoma, unspecified, unspecified site |
| C84.A1 | Cutaneous t-cell lymphoma, unspecified lymph nodes of head, face, and neck |
| C84.A2 | Cutaneous t-cell lymphoma, unspecified, intrathoracic lymph nodes |
| C84.A3 | Cutaneous t-cell lymphoma, unspecified, intra-abdominal lymph nodes |
| C84.A4 | Cutaneous t-cell lymphoma, unspecified, lymph nodes of axilla and upper limb |
| C84.A5 | Cutaneous t-cell lymphoma, unspecified, lymph nodes of inguinal region and lower limb |
| C84.A6 | Cutaneous t-cell lymphoma, unspecified, intrapelvic lymph nodes |
| C84.A7 | Cutaneous t-cell lymphoma, unspecified, spleen |
| C84.A8 | Cutaneous t-cell lymphoma, unspecified, lymph nodes of multiple sites |
| C84.A9 | Cutaneous t-cell lymphoma, unspecified, extranodal and solid organ sites |
| C84.Z | Other mature t/Nk-cell lymphomas |
| C84.Z0 | Other mature t/Nk-cell lymphomas, unspecified site |
| C84.Z1 | Other mature t/Nk-cell lymphomas, lymph nodes of head, face, and neck |
| C84.Z2 | Other mature t/Nk-cell lymphomas, intrathoracic lymph nodes |
| C84.Z3 | Other mature t/Nk-cell lymphomas, intra-abdominal lymph nodes |
| C84.Z4 | Other mature t/Nk-cell lymphomas, lymph nodes of axilla and upper limb |
| C84.Z5 | Other mature t/Nk-cell lymphomas, lymph nodes of inguinal region and lower limb |
| C84.Z6 | Other mature t/Nk-cell lymphomas, intrapelvic lymph nodes |
| C84.Z7 | Other mature t/Nk-cell lymphomas, spleen |
| C84.Z8 | Other mature t/Nk-cell lymphomas, lymph nodes of multiple sites |
| C84.Z9 | Other mature t/Nk-cell lymphomas, extranodal and solid organ sites |
| C85 | Other specified and unspecified types of non-hodgkin lymphoma |
| C85.1 | Unspecified b-cell lymphoma |
| C85.10 | Unspecified b-cell lymphoma, unspecified site |
| C85.11 | Unspecified b-cell lymphoma, lymph nodes of head, face, and neck |
| C85.12 | Unspecified b-cell lymphoma, intrathoracic lymph nodes |
| C85.13 | Unspecified b-cell lymphoma, intra-abdominal lymph nodes |
| C85.14 | Unspecified b-cell lymphoma, lymph nodes of axilla and upper limb |
| C85.15 | Unspecified b-cell lymphoma, lymph nodes of inguinal region and lower limb |
| C85.16 | Unspecified b-cell lymphoma, intrapelvic lymph nodes |
| C85.17 | Unspecified b-cell lymphoma, spleen |
| C85.18 | Unspecified b-cell lymphoma, lymph nodes of multiple sites |
| C85.19 | Unspecified b-cell lymphoma, extranodal and solid organ sites |
| C85.2 | Mediastinal (thymic) large b-cell lymphoma |
| C85.20 | Mediastinal (thymic) large b-cell lymphoma, unspecified site |
| C85.21 | Mediastinal (thymic) large b-cell lymphoma, lymph nodes of head, face, and neck |
| C85.22 | Mediastinal (thymic) large b-cell lymphoma, intrathoracic lymph nodes |
| C85.23 | Mediastinal (thymic) large b-cell lymphoma, intra-abdominal lymph nodes |
| C85.24 | Mediastinal (thymic) large b-cell lymphoma, lymph nodes of axilla and upper limb |
| C85.25 | Mediastinal (thymic) large b-cell lymphoma, lymph nodes of inguinal region and lower limb |
| C85.26 | Mediastinal (thymic) large b-cell lymphoma, intrapelvic lymph nodes |
| C85.27 | Mediastinal (thymic) large b-cell lymphoma, spleen |
| C85.28 | Mediastinal (thymic) large b-cell lymphoma, lymph nodes of multiple sites |
| C85.29 | Mediastinal (thymic) large b-cell lymphoma, extranodal and solid organ sites |
| C85.8 | Other specified types of non-hodgkin lymphoma |
| C85.80 | Other specified types of non-hodgkin lymphoma, unspecified site |
| C85.81 | Other specified types of non-hodgkin lymphoma, lymph nodes of head, face, and neck |
| C85.82 | Other specified types of non-hodgkin lymphoma, intrathoracic lymph nodes |
| C85.83 | Other specified types of non-hodgkin lymphoma, intra-abdominal lymph nodes |
| C85.84 | Other specified types of non-hodgkin lymphoma, lymph nodes of axilla and upper limb |
| C85.85 | Other specified types of non-hodgkin lymphoma, lymph nodes of inguinal region and lower limb |
| C85.86 | Other specified types of non-hodgkin lymphoma, intrapelvic lymph nodes |
| C85.87 | Other specified types of non-hodgkin lymphoma, spleen |
| C85.88 | Other specified types of non-hodgkin lymphoma, lymph nodes of multiple sites |
| C85.89 | Other specified types of non-hodgkin lymphoma, extranodal and solid organ sites |
| C85.9 | Non-hodgkin lymphoma, unspecified |
| C85.90 | Non-hodgkin lymphoma, unspecified, unspecified site |
| C85.91 | Non-hodgkin lymphoma, unspecified, lymph nodes of head, face, and neck |
| C85.92 | Non-hodgkin lymphoma, unspecified, intrathoracic lymph nodes |
| C85.93 | Non-hodgkin lymphoma, unspecified, intra-abdominal lymph nodes |
| C85.94 | Non-hodgkin lymphoma, unspecified, lymph nodes of axilla and upper limb |
| C85.95 | Non-hodgkin lymphoma, unspecified, lymph nodes of inguinal region and lower limb |
| C85.96 | Non-hodgkin lymphoma, unspecified, intrapelvic lymph nodes |
| C85.97 | Non-hodgkin lymphoma, unspecified, spleen |
| C85.98 | Non-hodgkin lymphoma, unspecified, lymph nodes of multiple sites |
| C85.99 | Non-hodgkin lymphoma, unspecified, extranodal and solid organ sites |
| C86 | Other specified types of t/Nk-cell lymphoma |
| C86.0 | Extranodal Nk/t-cell lymphoma, nasal type |
| C86.1 | Hepatosplenic t-cell lymphoma |
| C86.2 | Enteropathy-type (intestinal) t-cell lymphoma |
| C86.3 | Subcutaneous panniculitis-like t-cell lymphoma |
| C86.4 | Blastic Nk-cell lymphoma |
| C86.5 | Angioimmunoblastic t-cell lymphoma |
| C86.6 | Primary cutaneous Cd30-positive t-cell proliferations |
| C88.0 | Waldenstrom macroglobulinemia |
| C88.4 | Extranodal marginal zone b-cell lymphoma of mucosa-associated lymphoid tissue [MALt-lymphoma] |
| C91.5 | Adult t-cell lymphoma/leukemia (HTLv-1-associated) |
| C91.50 | Adult t-cell lymphoma/leukemia (HTLv-1-associated) not having achieved remission |
| Penile carcinoma | |
| C60 | Malignant neoplasm of penis |
| C60.0 | Malignant neoplasm of prepuce |
| C60.1 | Malignant neoplasm of glans penis |
| C60.2 | Malignant neoplasm of body of penis |
| C60.8 | Malignant neoplasm of overlapping sites of penis |
| C60.9 | Malignant neoplasm of penis, unspecified |
| Pleural malignant effusion | |
| J91.0 | Malignant pleural effusion |
| Squamous cell carcinoma of head and neck | |
| C44.02 | Squamous cell carcinoma of skin of lip |
| C44.12 | Squamous cell carcinoma of skin of eyelid, including canthus |
| C44.121 | Squamous cell carcinoma of skin of unspecified eyelid, including canthus |
| C44.122 | Squamous cell carcinoma of skin of right eyelid, including canthus |
| C44.1221 | Squamous cell carcinoma of skin of right upper eyelid, including canthus |
| C44.1222 | Squamous cell carcinoma of skin of right lower eyelid, including canthus |
| C44.129 | Squamous cell carcinoma of skin of left eyelid, including canthus |
| C44.1291 | Squamous cell carcinoma of skin of left upper eyelid, including canthus |
| C44.1292 | Squamous cell carcinoma of skin of left lower eyelid, including canthus |
| C44.22 | Squamous cell carcinoma of skin of ear and external auricular canal |
| C44.221 | Squamous cell carcinoma of skin of unspecified ear and external auricular canal |
| C44.222 | Squamous cell carcinoma of skin of right ear and external auricular canal |
| C44.229 | Squamous cell carcinoma of skin of left ear and external auricular canal |
| C44.32 | Squamous cell carcinoma of skin of other and unspecified parts of face |
| C44.320 | Squamous cell carcinoma of skin of unspecified parts of face |
| C44.321 | Squamous cell carcinoma of skin of nose |
| C44.329 | Squamous cell carcinoma of skin of other parts of face |
| C44.42 | Squamous cell carcinoma of skin of scalp and neck |
| Squamous cell carcinoma of vulva | |
| C51 | Malignant neoplasm of vulva |
| C51.0 | Malignant neoplasm of labium majus |
| C51.1 | Malignant neoplasm of labium minus |
| C51.2 | Malignant neoplasm of clitoris |
| C51.8 | Malignant neoplasm of overlapping sites of vulva |
| C51.9 | Malignant neoplasm of vulva, unspecified |
| Testicular germ cell tumor | |
| C62 | Malignant neoplasm of testis |
| C62.0 | Malignant neoplasm of undescended testis |
| C62.00 | Malignant neoplasm of unspecified undescended testis |
| C62.01 | Malignant neoplasm of undescended right testis |
| C62.02 | Malignant neoplasm of undescended left testis |
| C62.1 | Malignant neoplasm of descended testis |
| C62.10 | Malignant neoplasm of unspecified descended testis |
| C62.11 | Malignant neoplasm of descended right testis |
| C62.12 | Malignant neoplasm of descended left testis |
| C62.9 | Malignant neoplasm of testis, unspecified whether descended or undescended |
| C62.90 | Malignant neoplasm of unspecified testis, unspecified whether descended or undescended |
| C62.91 | Malignant neoplasm of right testis, unspecified whether descended or undescended |
| C62.92 | Malignant neoplasm of left testis, unspecified whether descended or undescended |
Formulary Reference Tool